Efficacy and safety of the nucleoside analog GS-441524 for treatment of cats with naturally occurring feline infectious peritonitis

2/13/2019, Journal of Feline Medicine and Surgery; Translation 10.2.2021
Original article: Efficacy and safety of the nucleoside analog GS-441524 for treatment of cats with naturally occurring feline infectious peritonitis
Niels C Pedersen, Michel Perron, Michael Bannasch, Elizabeth Montgomery, Eisuke Murakami, Molly Liepnieks, and Hongwei Liu

Abstract

Goals

The aim of this study was to determine the safety and efficacy of the nucleoside analog GS-441524 for cats suffering from various forms of naturally occurring feline infectious peritonitis (FIP).

Methods

Cats ranged in age from 3.4 to 73 months (mean 13.6 months); 26 cats had wet or mixed FIP, 5 dry form FIP. Cats with severe neurological and ocular FIP were not included in the study. The group started with GS-441524 at a dose of 2.0 mg / kg SC q24h for at least 12 weeks, which increased to 4.0 mg / kg SC q24h when indicated.

The results

Four of the 31 cats that had severe disease died or were euthanized within 2-5 days and the fifth cat after 26 days. The remaining 26 cats completed the planned 12 or more weeks of treatment. Eighteen of these 26 cats remain healthy at the time of publication (OnlineFirst, February 2019) after one round of treatment, while eight others suffered relapses within 3-84 days. Six of the relapses were non-neurological and two were neurological. Three of the eight rats were treated again with the same dose, while the five cats were increased from 2.0 to 4.0 mg / kg every 24 hours. Five cats treated with a second higher dose, including one with neurological disease, responded well and were healthy at the time of publication. However, one of the three cats re-treated with the original lower dose relapsed with neurological disease and was euthanized, while the two remaining cats responded favorably but a second relapse occurred. These two cats were successfully treated for the third time at a higher dose, which resulted in 25 long-term surviving cats. One of the 25 successfully treated cats was subsequently euthanized due to probable unrelated heart disease, while 24 remained healthy.

Conclusion and meaning

GS-441524 has been shown to be safe and effective in the treatment of FIP. The optimal dose was 4.0 mg / kg SC q24h for at least 12 weeks.

Keywords: Nucleoside analogue, GS-441524, feline infectious peritonitis, FIP, clinical study

Introduction

Drugs that inhibit viral replication have become a focal point in the treatment of human acute and chronic RNA and DNA infections. However, the development of interest in antiviral drugs for animal infections has been much slower. This is especially true for cats, which suffer from several chronic viral infections similar to humans. Infectious agents include feline leukemia and immunodeficiency virus (FeLV and FIV), feline herpesvirus (FHV), virulent systemic calicivirus, and coronavirus causing feline infectious peritonitis (FIPV). FeLV and FIV infections can be kept under control through testing, isolation and / or vaccination. The FHV-associated disease was the first feline viral infection to use an antiviral agent for treatment. Highly fatal systemic calicivirus affects only a small number of cats. FIPV infection is the best candidate for the development of antiviral drugs because vaccines are ineffective, the environment with many cats makes it very difficult to prevent and kills 0.3-1.4% cats worldwide.

The emergence of exotic diseases such as Ebola, Middle East Respiratory Syndrome (MERS) and Severe Acute Respiratory Syndrome (SARS) in humans has prompted intensive research into drugs that inhibit RNA replication. One of the most promising antiviral drugs for nascent RNA viruses is the prodrug adenosine nucleoside monophosphate GS-5734 (Remdesivir; Gilead Sciences). GS-5734 demonstrated efficacy in experimental Ebola in rhesus monkeys and inhibited both epidemic and zoonotic coronaviruses in tissue cultures and mouse infectious models. These promising findings initiated research into GS-5734 and its original nucleoside GS-441524 against FIPV infection in cats. GS-441524 and GS-5734 have comparable EC50 (1.0 μM) and CC50 (> 100 μM) values against FIPV in feline cells. Therefore, it was decided to focus on the less chemically complex GS-441524 for further testing with laboratory cats. A pharmacokinetic study in two laboratory cats showed sustained and effective plasma levels of GS-441524 over 24 hours after a dose administered subcutaneously (SC) or intravenously (IV). These results were extended to 10 laboratory cats with experimentally induced abdominal effusion feline infectious peritonitis (FIP). This study demonstrated that GS-441524 is highly effective against experimental FIP, paving the way for this clinical study.

The aim of this study was to demonstrate the safety and efficacy of GS-441524 in the treatment of cats with naturally occurring FIP. Small molecule drugs, such as GS-441524, weigh <900 daltons and are approximately 1 nm in size and can easily penetrate cells and interact with key target molecules. Unlike previously published substances or drugs that inhibit FIPV by inhibiting cellular processes by viruses used for their replication, small molecules such as GS-441524 interfere directly with virus-encoded replication processes.

Materials and methods

Preparation of the drug

GS-441524 was provided by Gilead Sciences as a pure and highly stable powder, which was diluted to a concentration of 10 or 15 mg / ml in 5% ethanol, 30% propylene glycol, 45% PEG 400, 20% water (pH 1.5 with HCl). The solution was placed in sterile 50 ml glass vials in which it was shaken until dissolved and then subjected to a sonic water bath for 5 to 20 minutes until clear. The diluted drug was refrigerated and used within 3-4 weeks.

Study concept

This study was conducted in accordance with Protocols 19336 and 19863, approved by the Institutional Committee on the Care and Use of Animals and the Clinical Trials Evaluation Committee of the Veterinary Teaching Hospital of the University of California, Davis. The institutional rules exclude the use of sick cats from shelters or similar establishments, due to the requirement of legal ownership / adoption and treatment under specific conditions with the consent of the owner (supplementary material). The study did not include a control group because there is no effective comparative treatment. The placebo group was not included either, as in vitro and in vivo preparatory studies indicated that GS-441524 would be safer and more effective than any treatment.

Case selection and diagnosis confirmation

Cats with FIP were received from owners or their veterinarians who were looking for current treatment options or access to a previous study of antiviral drugs. The initial diagnosis of FIP was based primarily on characteristic signaling, clinical history and symptoms of the disease, results of routine laboratory tests, and examination of abdominal or thoracic effusions. A more definitive diagnosis based on RT-PCR or immunohistochemistry was desirable, but not a prerequisite for inclusion. Cats with overt ocular or neurological disease were excluded due to doubts about the ability of antiviral drugs, including GS-441524, to cross the blood-brain or blood-eye barrier.

31 cats and their owners were admitted to the study (Table 1). Owners or representatives of 26 cats came for initial treatment directly to UC Davis and five owners and their cats (CT59, CT73, CT76, CT78, CT80) were treated by a local veterinarian. The cats present at UC Davis were re-evaluated, their FIP diagnosis was re-confirmed on the basis of signaling, clinical history, physical examination, results of previous laboratory tests and complete blood count (CBC), serum protein and effusion analyzes. Thoracic or abdominal effusion in cats with wet FIP was confirmed positive for FIPV 7b RNA by RT-PCR. Cats with signs of non-fusion FIP were further tested by abdominal and thoracic ultrasonography for primary lesions. The eye disease was confirmed by the VMTH Ophthalmology Service, UC Davis. The neurological condition in cases with possible symptoms of central nervous system disease was evaluated by the VMTH neurological service.

Table 1
List of 31 cats included in the test, including laboratory designation, cat name, breed, clinical form of infectious peritonitis (FIP) and date of diagnosis

IDNameDate of birthTribeGenderOriginDate of diagnosisFIP form
CT52Moon9.1.2017SavannahFBreeder24.4.2017Abdominal effusion
CT53Ice Bear2.8.2016DLHMCRescue team5.5.2017Abdominal effusion
CT54Charolett11.7.2016SiberianFBreeder15.4.2017Abdominal effusion
CT55Dempsey26.6.2016DSHMCRescue team15.4.2017Abdominal effusion
CT56Mudsa1.7.2016DSHMCShelter12.5.2017Abdominal effusion
CT57Boone31.10.2016DSHFSRescue team8.5.2017Abdominal effusion
CT58Justyna17.4.2016RagdollFBreeder25.5.2017Abdominal effusion
CT59Bubba11.4.2011DLHMCWandering10.4.2017Abdominal non-fusion
CT60Joey25.7.2016DSHMCRescue team20.5.2017Abdominal effusion
CT61Hudson1.7.2016DSHMCRescue team29.5.2017Thoracic effusion
CT62Luca10.3.2016DSHMCRescue team30.5.2017Abdominal effusion
CT63Bao Bao6.11.2016DSHMCRescue team3.6.2017Abdominal effusion
CT64Cedrick27.6.2016DSHMCRescue team22.5.2017Abdominal non-fusion
CT65Mona14.3.2016Exotic SH / PersianFBreeder11.6.2017Thoracic effusion
CT66Squeekers7.6.2016DSHFSShelter14.6.2017Abdominal effusion
CT67Double2.3.2016RagdollFSBreeder20.6.2017Abdominal effusion
CT68Tuckerman8.5.2016Maine CoonMCRescue team22.6.2017Abdominal effusion
CT69Danny16.6.2015SnowshoeMCShelter22.6.2017Thoracic effusion
CT70Tolstoy1.8.2014DSHMCRescue team25.6.2017Abdominal effusion
CT71Amadeus29.6.2016DSHMCWandering20.6.2017Thoracic effusion
CT72Bella25.2.2017British SHFBreeder20.6.2017Abdominal effusion
CT73Siersha8.8.2015DSHFSShelter21.6.2017Abdominal non-fusion
CT74Maive4.3.2017SiberianFSBreeder7.7.2017Abdominal effusion
CT75Lucy31.3.2017DSHFRescue team10.7.2017Abdominal effusion
CT76Pie20.7.2016Exotic SHMBreeder28.6.2017Abdominal effusion
CT77Mila15.3.2017SiberianFSBreeder3.7.2017Abdominal effusion
CT78Polly1.3.2016DSHMCRescue team22.7.2017Abdominal non-fusion
CT79Oona21.9.2016HimalayanFBreeder18.7.2017Chest non-fusion
CT80Fezzik17.10.2016DLHMCWandering25.7.2017Abdominal effusion
CT81Jewelkat8.9.2016PersianFSBreeder1.8.2017Thoracic effusion
CT82Tiko8.4.2016DSHMCRescue team6.8.2017Abdominal effusion
F = uncastrated female; FS = castrated female; M = male uncastrated; MC = castrated male; DLH = domestic longhair; DSH = domestic shorthair; SH = short-haired;

Treatment regimen

Based on previous tissue culture experiments and pharmacokinetic studies in laboratory cats, the initial dosing regimen for GS-441524 was set at 2.0 mg / kg SC q24h. Based on experience with the 3CL protease inhibitor GC376 against naturally occurring FIP, a minimum treatment period of 12 weeks was established. Treatment was extended by one or more weeks in cats that still had abnormal serum protein levels. In later stages of the study, the dose was increased from 2.0 to 4.0 mg / kg in cases where treatment had to be prolonged or when the disease had relapsed. Every 4 weeks, a new dose of 1 or 3 ml Luer lock syringes with 1 inch Luer 22G (0.7x25mm) Luer needles was sent to the owners. The syringes were stored in a refrigerator and warmed to room temperature before administration. Injections were given along the spine from 2 cm behind the shoulder blades to half of the lumbar region and halfway down to the adjacent chest and hips.

Monitoring during the initial treatment period

At the time of entry into testing, the cats had stopped all treatment that was not necessary - antibiotics, corticosteroids, interferons, pentoxifylline, non-steroidal anti-inflammatory drugs, or painkillers. During their stay at UC Davis, cats were monitored every 12 hours for temperature, appetite, activity, urination and defecation. Blood was collected at 1-3 day intervals to evaluate hematocrit, total protein, bilirubin, white blood cell count and differential white blood cell count.

Ascites samples were taken initially and then taken at one or more daily intervals for as long as possible and tested for FIPV 7b RNA transcript levels by quantitative (q) RT-PCR (IDEXX molecular diagnostics). Formalin-fixed tissue sections from five dissected cats were subjected to immunohistochemistry for FIPV nucleocapsid protein.

Monitoring of initial and long-term response to treatment

Cats were released for home treatment when a significant favorable response to treatment was noted, usually within 3-5 days. During this period, owners were instructed on the proper administration of subcutaneous injections and were encouraged to continue daily records of body temperature, activity, appetite, defecation and urination, and weekly body weight measurements. CBC and serum chemical panel were performed at monthly intervals by local veterinarians or during VMTH visits. Any abnormal symptoms or behaviors should be recorded and reported immediately. Reasonable euthanasia was usually performed by the owner's veterinarian or, if possible, at UC Davis. The bodies were immediately cooled and sealed in plastic bags, and sent within 2 or fewer days in ice-cooled containers to UC Davis by express mail. Autopsies were performed by one of the authors (ML) at the Anatomic Pathology Service, School of Veterinary Medicine, UC Davis. The owner's request for the final disposition of the body was respected.

The results

Disease signaling and presentation

The study included 31 cats aged 3.4 to 73 months (mean 13.6 months) (Table 1). Eighteen cats were domestic short-haired and long-haired, 13 cats represented representatives of 10 different breeds (Table 1). Domestic cats were adopted from cat rescue organizations (n = 13), shelters (n = 2) or stray cats from the area (n = 3). The study included 14 females (7 neutered; 7 neutered) and 17 males (1 neutered; 16 neutered).

Twenty-six of the 31 cats had wet FIP (6 thoracic, 20 abdominal). Five cats had non-fusion FIP; four of them (CT59, CT64, CT73, CT78) with disease located in the abdomen (mesenteric and ileo / cecal / colic lymph nodes) and one (CT79) in the chest (lungs, hilar lymph nodes) (Table 1). Four additional cats showed signs of earlier dry FIP, which turned into an effusion form (CT57, CT65, CT67, CT71) (Table 1). Gross symptoms of eye disease corresponding to FIP were confirmed by ophthalmoscopic examination in three of the 31 cats (CT56, CT65, CT71). Two cats (CT71, CT80) reluctantly or were unable to jump to elevated sites at all, indicating neurological impairment.

Treatment results

Four cats were euthanized (CT62, CT72, CT75) or died (CT56) during the first 2-5 days due to serious illness and other complications, and the fifth cat was euthanized (CT54) after 26 days due to lack of response to treatment (Figure 1). Treatment was uninterrupted, with the exception of three cats who were given a two-week rest period at week 4 (cat CT80) or week 8 (cat CT53, CT71) due to injection problems and skin reactions (Figure 1). After the second relapse, the CT53 cat was treated for 8 and not 12 weeks due to an increase in blood urea and an increase in serum levels of symmetric dimethylarginine (SDMA).

Figure 1.
Treatment time scale and clinical outcome of 31 cats enrolled in clinical study GS-441524. The treatment period is indicated by a solid line (dose 2 mg / kg) or a dashed line (dose 4 mg / kg). Asterisks indicate a relapse point. The end date of treatment for cats that have achieved permanent clinical remission is indicated in parentheses. The time point and cause of death are marked with a cross

The clinical response of the 26 cats that completed at least 12 weeks of treatment was dramatic. The fever usually resolved within 12-36 hours (Figure 2), along with a significant increase in appetite, activity levels, and weight gain on a daily basis. Abdominal effusions quickly disappeared within 1-2 weeks, starting at about 10-14. the day after starting treatment. Cats with thoracic effusions, usually showing shortness of breath, were sucked out by practical private veterinarians before the pleural effusions were aspirated before arriving at UC Davis. Residual shortness of breath and thoracic effusion responded quickly to treatment and were no longer visible at all after 7 days. Jaundice resolved slowly over 2–4 weeks, with a decrease in hyperbilirubinemia. Signs of eye disease began to disappear within 24-48 hours and ceased to be apparent on the outside even for ophthalmoscopic examination within 7-14 days. Enlarged mesenteric and ileo / cecal / colic lymph nodes began to shrink during treatment. According to the owners' estimates, all 26 cats looked normal or almost normal on the outside after 2 weeks of treatment. After 2 weeks of treatment, the emphasis was on monitoring several blood test parameters. Key values included hematocrit, total white blood cell count, absolute lymphocyte count, total serum protein, serum globulin, serum albumin, and albumin: globulin ratio (A: G).

Figure 2.
Mean (solid line) and 1 SD (standard deviation) (dashed) body temperatures during the first 5 days of GS-441524 treatment. The normal temperature range for cats is 37.7-39.1 ° C (100-102.5 ° F). Temperatures dropped to the normal range within 12-36 hours of treatment

Eighteen of the 26 cats that received at least 12 weeks of uninterrupted primary treatment required no further treatment. However, eight other cats suffered disease relapses within 3–84 days (mean 23 days) (Figure 1). This group included three cats that temporarily discontinued initial treatment (CT53, CT71, CT80), and five cats (CT53, CT57, CT60, CT68, CT73) that required extended primary treatment (Figure 1). The disease relapses in 2/8 cats (CT57, CT71) were apparently neurological in nature with high fever and strong posterior ataxia and incoordination, while the disease relapses in the remaining six cats consisted mainly of fever, anorexia and decreased activity. Only one cat (CT60) had an obvious abdominal discharge during the relapse. One cat (CT57) was euthanized 2 weeks after relapse with neurological symptoms that did not respond to the second round of treatment.

In eight cats, it was decided to increase the dose of GS-441524 from 2.0 to 4.0 mg / kg, either due to prolongation of treatment (CT77, CT80) or due to one (CT60, CT68, CT71, CT73) or two relapses ( CT53, CT63), or because the relapse had a neurological form (CT71). All eight cats responded positively to the booster regimen.

A total of 25/26 cats treated for 12 weeks or more achieved permanent remission of FIP, although one subsequently died of an unrelated heart problem (see "Autopsy Findings"). The longest surviving cats at the time of publication (OnlineFirst, February 2019) stopped treatment in August 2017 and the shortest in May 2018, all after the end of the observation period, in which relapse could still occur (ie 84 days after the end of treatment). The 24 surviving cats will be carefully monitored for recurrence of symptoms and will be regularly tested for total protein, globulin, albumin and A: G ratios during the first year. Less intensive monitoring will be performed for the rest of the cats' lives. Owners were advised to avoid unnecessary strain on cats during the first 3 months, even though four cats (CT52, CT58, CT65, CT79) and one cat (CT76) underwent trouble-free castration.

Indicators of favorable response to treatment

The simplest long-term measure of treatment effectiveness was body weight. Weight gain of 20–120% occurred during and after treatment, even in cats that were 1 year or older at the time of diagnosis. Significant growth also appeared in younger cats, as their owners independently noted. These significant post-treatment growth accelerations suggested that FIP was subclinical in many cats for some time before diagnosis and affected their growth. CBC (hematology) and chemical profile (biochemistry) have also been shown to monitor the later effects of treatment and to observe possible drug toxicities.

CBCs (Hematology)

Cats showed an increased white blood cell count, which fell to normal during the first 2 weeks of treatment (Figure 3a). Lymphopenia recorded at the time of admission disappeared during the first week of treatment (Figure 3b). Mild to moderate anemia was observed on admission, resulting in hematocrit (PCV) (Figure 4). Hematocrit did not return to normal until 6-8 weeks of treatment. Absolute total white blood cell and lymphocyte counts were the only significant values during the first week of treatment, while PCV provided a more accurate picture of the course of treatment during the first 8 weeks.
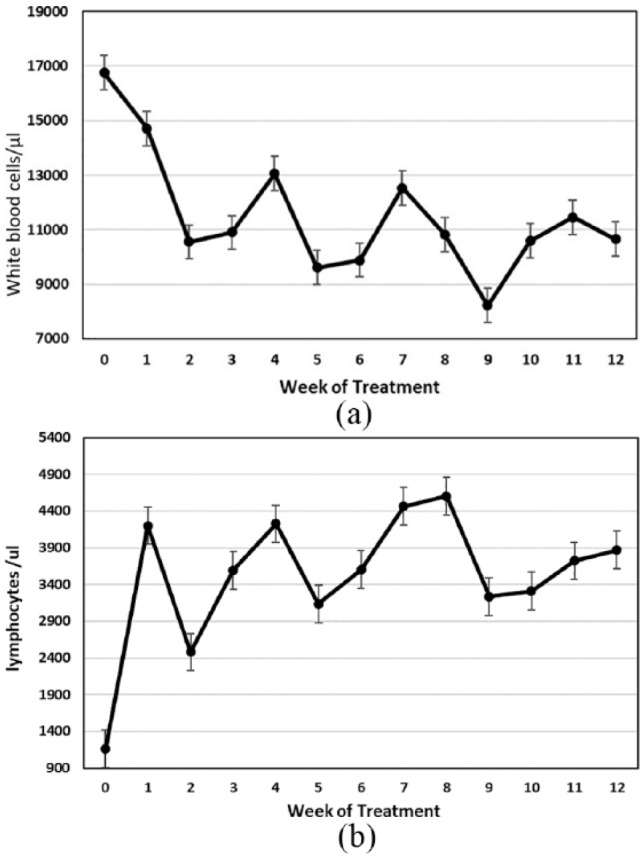
Figure 3.
(a) Mean standard deviation white blood cell count in 26 cats that completed a primary treatment regimen for 12 weeks or more. (b) Mean absolute lymphocyte count in blood with standard deviation in 26 cats that had completed at least 12 weeks of treatment
Figure 4.
Hematocrit (PCV) with a standard deviation for 26 cats that have completed at least 12 weeks of treatment. The dotted line indicates the growth trend of PCV over time

Serum protein changes

Cats with FIP often showed higher than normal total serum protein levels, high serum globulin levels, low serum albumin levels, and low A: G ratios (Figures 5-7). Serum protein abnormalities progressively improved and reached normal values after 8-10 weeks of treatment (Figures 5-7). Total protein levels were the least informative, indicating a low R2 (0.1883) trend line (Figure 5). However, 3 weeks after the start of treatment, there was a dramatic and transient increase in total protein levels (Figure 5). This phenomenon was related to an increase in serum globulins (Figure 6a) at a time of rapid regression of abdominal effusions.

Figure 5.
Mean serum total protein levels and standard deviation for 26 cats that have completed at least 12 weeks of treatment
Figure 6.
(a) Mean serum globulin levels and standard deviation for 26 cats that have completed at least 12 weeks of treatment. (b) Mean serum albumin levels and standard deviation for 26 cats that have completed at least 12 weeks of treatment
Figure 7.
Mean albumin: globulin (A / G) ratios and standard deviation for 26 cats that have completed at least 12 weeks of treatment

Plasma globulin levels increased during the first 3 weeks of treatment, peaked and then slowly decreased to a maximum reference value of 4.5 g / dl or less by week 9 (Figure 6a). Although globulin levels appear to reflect treatment status over time, a low R2 (0.3621) indicated that this was a less reliable indicator of treatment progress.

Serum albumin levels of 26 cats treated for at least 12 weeks were usually low (⩽3.2 g / dl) at the time of treatment (Figure 6b). Albumin levels then increased slowly and reached normal levels after 8 weeks. The trend line for this increase in albumin was high R2 (0.79), making serum albumin levels as well as PCV a good indicator of treatment progress. As expected, the A: G ratio showed an equally strong trend line over time and around the 8th week of treatment the level exceeded 0.70 (Figure 7).

Decreased viral RNA levels in ascitic fluid cells in association with treatment

During the first 2-9 days of antiviral treatment, sequential ascites samples were taken from eight cats and tested for viral RNA levels by qRT-PCR (Table 2). The most reliable source of FIPV RNA was whole effluents or their cell fractions. In 7/8 cats, viral RNA levels dropped within 2-5 days, often to undetectable levels. One cat (CT54) did not show a significant decrease in viral RNA levels within 9 days.

Table 2
Levels of feline infectious peritonitis 7b RNA transcription in whole ascites or ascitic fluid cell fraction during initial treatment GS-441524

Sample IDTreatment daysSample typeCopies of viral RNA / ml
CT520Ascites9.44 × 104
3AscitesUndetectable
CT540Ascites8.49 × 105
2Ascites6.97 × 104
4Ascites2.44 × 103
7Ascites2.07 × 103
9Ascites6.46 × 104
CT620Ascites5.96 × 103
2Ascites1.53 × 103
8AscitesUndetectable
CT740Cells6.51 × 106
2Cells3.39 × 105
CT750Cells9.08 × 106
3Cells4.75 × 105
4Cells2.50 × 105
CT770Ascites5.47 × 104
2Ascites3.93 × 103
CT800Ascites4.10 × 103
2AscitesUndetectable
CT820Ascites1.13 × 104
5AscitesUndetectable

Side effects observed during and after treatment

Limited injection site reactions. Two types of injection site reactions have been observed and it has not been established whether they were due to the drug, the diluent or both. Immediate responses to pain were manifested by vocalization, occasional growling, and postural changes lasting 30-60 seconds. These initial reactions eased over time as owners became more skilled at injecting and cats gradually adapted to this routine. Sixteen of the 26 cats treated experienced injection site reactions (Table 3). Reactions were most common during the first 4 weeks and progressed to open wounds in only 7/16 cats. Ulcerations healed within 2 weeks by trimming the surrounding hair and gently cleaning the wound with a cotton swab soaked in one part household hydrogen peroxide and two parts water twice a day. Only three cats had noticeable scars at the injection sites.

Table 3
Injection site reactions in 16 of 26 cats treated with GS-441524 for 12 weeks or more

Cat IDSuperficial lesionsOpen woundsScars
CT53310
CT58100
CT60002
CT61500
CT63220
CT64101
CT65911
CT66320
CT68400
CT71510
CT73710
CT74310
CT761000
CT78700
CT79200
CT82200
Most lesions were superficial and included the epidermis and did not require any treatment, while some progressed to open wounds that healed within 2 weeks of topical treatment. Some reactions left small permanent scars

Systemic drug reactions. GS-441524 treatment was remarkably safe for a total of 12-30 weeks. No long-term abnormalities were observed in CBC values (Figures 3 and 4). Liver and kidney function tests and amylase / lipase levels remained normal during and after treatment (Supplemental Figures S1 - S3). The only exception was the CT53 cat, which had a progressive increase in blood urea (BUN) to 35 mg / dl (reference interval [RI] 16–37 /g / dl) and a sudden increase in SDMA (20 µg / dl) (RI 0- 14 /g / dl) after 8 weeks in the third round of treatment in a 4 mg / kg booster regimen. Although these symptoms were still mild in nature, it was decided to discontinue treatment. These abnormalities were no longer present when tested 1 month later and the cat is currently in remission.

Autopsy findings

Four cats (CT56, CT62, CT72, CT75) were euthanized or died within 2-5 days of study entry, and necropsies were performed on all but the CT75 cat. The fifth cat (CT54 cat) was euthanized after 26 days of treatment. All five of these cats had severe abdominal effusion disease. At CT54 and CT56, necropsy revealed evidence of extensive pyogranulomatous vasculitis involving the abdominal viscera, central nervous system, and eyes. In the CT56 cat, the ileal wall was also compromised in the area of ​​dense infiltrate and secondary bacterial sepsis. The CT72 cat had severe abdominal pyogranulomatous vasculitis with moderate to severe peripheral edema and adrenal cortex mineralization. The CT62 cat suffered from severe pyogranulomatous and fibrinosuppurative peritonitis, which was complicated by acute gastric perforation associated with plant material and intralesional bacteria suggestive of sepsis. The CT75 cat exhibited a chronic form of FIP characterized by severe growth retardation, massively low protein / low cell effusion, accelerated cardiac function suggestive of impaired cardiac function, and moderate peripheral edema. The echocardiogram showed bilateral atrial enlargement, but no sign of primary heart disease. The cat appeared to respond to GS-441524 and was released. The cat fell into shock 2 days later and was euthanized without autopsy.

At the time of necropsy of CT56, CT72 and CT75 cats, no FIPV virus was detected using qRT-PCR, although pre-treatment ascites samples were positive. Cat ascites CT54 showed a positive qRT-PCR result throughout treatment (Table 2) and the tissues were still immunohistochemically positive at the time of necropsy.

After successfully completing one or more rounds of treatment, two more cats were euthanized. The CT57 cat was normal after one round of treatment, but relapsed with severe neurological symptoms 2 weeks later. The cat did not respond to re-treatment and was killed. Lesions typical of FIP were found in the brain and abdomen, but were negative for FIPV determined by immunohistochemistry for nucleocapsid protein or for 7b RNA by qRT-PCR. The CT80 cat was successfully treated for effusive abdominal FIP, but 4 weeks later she developed severe hind leg and lower back pain. The cat was found to have a marked thickening of the left ventricular wall and septum, which caused severe ventricular narrowing (Figure 8). The microscopic appearance of the left ventricular wall was typical of congenital feline hypertrophic cardiomyopathy (HCM). No gross or microscopic FIP lesions were detected in the abdomen, chest, eyes, brain or spine, and neither FIPV nor FIPV RNA was detected by qRT-PCR.

Figure 8.
CT80 cat's heart section showing extreme left ventricular and septal wall hypertrophy and extreme ventricular narrowing

Discussion

GS-441524 is the second targeted antiviral drug tested for the treatment of FIP in the last 2-3 years after GC376. The two drugs inhibit viral replication in two very different ways, either by terminating viral RNA transcription or by blocking the cleavage of the viral polyprotein. Both processes are a well-known target for the treatment of some human viral diseases. A key issue is to compare nucleoside analogue treatment with viral protease inhibitor therapy. The two drugs gave virtually identical results in tissue culture studies and experimentally infected cats. However, the efficacy against naturally occurring FIP appeared to be higher with GS-441524 than with GC376. Six of the 20 cats treated with GC376 remain in remission to this day (Pedersen NC, unpublished data, 2018) compared to 25/31 cats treated with GS-441524. Diseases that did not respond to re-treatment occurred in 14/20 cats with GC376 but only in one cat treated with GS-441524. 8 of the 14 GC376-associated relapses were neurological, compared to 2/8 GS-441524 relapses. One of the two neurological relapses in cats treated with GS-441524 responded to re-treatment with a higher dose, whereas neurological relapses with GC376, even at an increased dose, were no longer treatable. Both treatments caused similar injection site reactions. Both drugs appear to be relatively safe, although GC376 interfered with the development of permanent teeth when given to younger kittens.

Although the results of the clinical study appear to favor GS-441524, some differences may have been affected by the way the two drugs were administered. The effectiveness of GC376 could be improved if all 20 cats were treated without interruption for 12 weeks, instead of being treated progressively over longer periods starting at only 2 weeks. Five of the six cats treated with GC376 were among the seven cats that were treated continuously for 12 weeks, while only one of the 13 cats treated once or more was treated for a shorter period of time. These shorter durations of treatment were necessary to determine the 12-week period used for all cats in this study. In addition, the GC376 clinical trial included fewer cats and was limited by limited drug delivery, making it difficult to test other dosing regimens. Therefore, GC376 should be further studied prior to any final comparison using a minimum of 12 weeks with a higher dose and more cats. It would also be important to evaluate both types of drugs in combination at some point in the future, as is the case with HIV / AIDS and hepatitis C.

Premature deaths should be considered in any study of this type, but how should they be considered in an efficacy analysis? Five premature deaths in this study were included in the GS-441524 efficacy analysis, but were excluded in study GC376. It is important to determine the status of the virus at the time of death to include deaths in the study. Viral RNA was not detected in three necropsed cats that died after 2-5 days of treatment with GS-441524, indicating that the drug was effective but the disease was at an advanced stage. This was not the case for the fourth dissected cat, which survived 26 days; viral RNA levels did not decrease throughout the treatment period and the symptoms of the disease did not improve. Therefore, it is possible that this cat died as a result of an unsuccessful cessation of virus replication. Resistance to GS-5734 (Remdesivir), a prodrug of GS-441524, has been associated with amino acid mutations in RNA polymerase and corrective exonuclease in tissue culture propagated coronaviruses. Whether this cat has developed similar resistance remains to be determined. Drug resistance was also observed in one cat in the GC376 test. Fortunately, none of the other cats in the current study showed signs of drug resistance. However, for future cats that do not respond at all or do not respond well to primary or secondary treatment, this option should be considered.

The initial dose of GS-441524 used in the present study was determined based on previous pharmacokinetic and experimental infectious studies with laboratory cats. These studies indicated that 2.0 and 5.0 mg / kg SC q24h for 14 days would be equally effective in the clinical study. Therefore, a dose of 2.0 mg / kg was chosen for clinical trials, as this would reduce drug consumption by 60%. Although this decision was confirmed in 18/26 cats, eight other cats either suffered relapses (two even twenty) or required a longer duration of treatment to get key blood levels back to normal. Therefore, a decision was made to increase the dose of GS-441524 from 2.0 mg / kg to 4.0 mg kg SC q24h in cats that relapsed or required prolonged treatment. The success rate of 4.0 mg / kg SC q24h in at least 12 such cats, as well as in one cat with a neurological disease, led us to the conclusion that this is a more effective dosage and should become the basis for future treatment.

It was important to monitor simple biological indicators of progress over ⩾ 12 weeks of treatment. HCT (PCV) levels, serum total protein, globulin and albumin levels, and the A: G ratio were identified as useful markers. Based on these parameters, it was shown that the cats had not yet fully recovered after 6-10 weeks of treatment. This finding confirmed the minimum 12-week duration of treatment determined in a previous GC376 clinical trial. Chronic anemia (inflammation anemia) affects 18-95% people with acute and chronic infections and is normocyte / normochromic and unrelated to iron deficiency. Plasma albumin levels were also a good indicator of disease activity, and low albumin and low HCT (PCV) are known to correspond to the incidence of chronic disease. Hyperglobulinemia in cats with FIP has been classified as infectious / inflammatory and is caused by an increase in all classes of gamma globulins and variable increases in the alpha-2 globulin fraction. The marked tendency of cats with FIP to high serum globulin and low albumin levels makes the A: G ratio a particularly good indicator of disease activity.

Purebred cats were not expected to respond as well to treatment due to their genetically impaired ability to respond immunologically to FIPV, and younger cats with wet FIP were expected to respond best to treatment. In this study, however, purebred cats eventually responded as well as regular cats, and the breeds represented by the cats in the study reflected the most popular current breeds. Older cats and cats with pure non-fusion FIP responded to GS-441524 as well as young cats and cats with wet FIP. Assuming that some cats with ocular and neurological diseases can also be treated with GS-441524, it can be said that no more manifestations of FIP may be considered incurable.

The safety profile of GS-441524 was impressive. Based on CBC and serum chemistry, no significant systemic signs of toxicity were observed during the total treatment periods of 12 to 30 weeks, with one possible exception. One cat (CT53) had a slight increase in BUN and SDMA in the 8th week of the third round of treatment and forced treatment to be stopped as a precautionary measure. Based on previous experience with GC376, there have been concerns about the effect of GS-441524 on the development of permanent teeth. Three cats (CT52, CT74, CT77) in this study were 4 months of age or younger and still had juvenile teeth and none showed any subsequent dental abnormalities. Injection site reactions were observed with GS-441524, but their number was remarkably low and easy to treat. It has not been established whether the drug, diluent or both are to blame. Diluent pH 1.5 was well below the FDA (Food and Drug Administration) minimum threshold of 4.5, but drugs of this type are difficult to dissolve and stabilize at a more physiologically acceptable pH. Nevertheless, more physiological diluents should be evaluated.

One cat in the study (CT80) had disturbing clinical signs. Although the cat showed effusive abdominal FIP, it also had long-term symptoms of vague hind limb curvature, low back pain, regular falling episodes, reluctance to jump to higher ground, and unexplained and transient behavioral changes. These symptoms led to the treatment of the cat long after the abdominal effusion disappeared. Finally, a decision was made to discontinue treatment and see if the characteristic symptoms of FIP returned. The cat was eventually euthanized and necropsied that it had a congenital HCM type and no residual FIP or viral RNA lesions in any tissues. Dilated cardiomyopathy has been reported in 17.6% HIV-infected people on chronic antiretroviral therapy. However, it was concluded that GS441524 was not the cause of the heart disease in this cat. Heart disease in this cat was hypertrophic in contrast to the dilatation form observed in HIV patients, and in addition, HCM is relatively common in shelter cats.

Conclusions

The results obtained from 31 cats treated with GS-441524 exceeded all expectations and suggest that FIP, regardless of signaling or disease form, is a treatable disease using nucleoside analogs. The study design and treatment parameters resulting from this limited clinical trial will be important for further efforts in the commercialization of this or similar anti-FIP drugs.

Additional material

Owner consent form

Figure S1. Mean liver enzyme levels (IU / L) in cats during treatment with GS-441524. No significant changes were observed throughout the treatment periods.
Figure S2. Mean serum lipase and amylase levels (IU / L) in cats during treatment with GS-441524. No significant changes were observed throughout the treatment periods.
Figure S3. Mean BUN and creatinine levels in cats during treatment with GS-441524. No significant changes were observed throughout the treatment periods.

Thanks

We thank the staff of the Center for Pet Health for their help in transporting medicines (Lyra Pineda-Nelson and Nancy Bei) and for presenting the data (Cynthia Echeverria). We are especially grateful to the many owners and 31 cats who took part in an emotional and demanding journey that exceeded all expectations. We are also grateful to the practical private veterinarians who helped with the regular blood tests and were there for us and their patients / owners when needed.

Notes

Received: December 28, 2018

Additional material: The following files are available: Client consent form.

Figure S1: Mean liver enzyme levels (IU / l) in cats during GS-441524 treatment. No significant changes were observed throughout the treatment periods.

Figure S2: Mean serum lipase and amylase levels (IU / l) in cats during GS-441524 treatment. No significant changes were observed throughout the treatment periods.

Figure S3: Mean urea and creatinine blood levels in cats during GS-441524 treatment. No significant changes were observed throughout the treatment periods.

Conflict of Interest: MP and EM are employees of Gilead Sciences, Foster City, CA, USA and have stakes in the company.

Funding: Financial support for this study was provided by the UC Davis Center for Animal Health, the Philip Raskin Fund in Kansas City, and numerous SOCK FIP donors as directed by Carol Horace. GS-441524 used in this experiment was provided by Gilead Sciences, Foster City, CA.

References

1.De Clercq, E, Li, G. Approved antiviral drugs over the past 50 years. Clin Microbiol Rev 2016; 29: 695–747.
Google Scholar | Crossref | Medline
2.Hartmann, K. Efficacy of antiviral chemotherapy for retrovirus-infected cats: what does the current literature tell us? J Feline Med Surg 2015; 17: 925–939.
Google Scholar | SAGE Journals | ISI
3.Thomasy, SM, Shull, O, Outerbridge, CA. Oral administration of famciclovir for treatment of spontaneous ocular, respiratory, or dermatologic disease attributed to feline herpesvirus type 1: 59 cases (2006–2013). J Am Vet Med Assoc 2016; 249: 526–538.
Google Scholar | Crossref | Medline
4.Pedersen, NC, Elliott, JB, Glasgow, A. An isolated epizootic of hemorrhagic-like fever in cats caused by a novel and highly virulent strain of feline calicivirus. Vet Microbiol 2000; 73: 281–300.
Google Scholar | Crossref | Medline | ISI
5.Kim, Y, Shivanna, V, Narayanan, S. Broad-spectrum inhibitors against 3C-like proteases of feline coronaviruses and feline caliciviruses. J Virol 2015; 89: 4942–4950.
Google Scholar | Crossref | Medline
6.Pedersen, NC, Kim, Y, Liu, H. Efficacy of a 3C-like protease inhibitor in treating various forms of acquired feline infectious peritonitis. J Feline Med Surg 2018; 20: 378–392.
Google Scholar | SAGE Journals | ISI
7.Pesteanu-Somogyi, LD, Radzai, C, Pressler, BM. Prevalence of feline infectious peritonitis in specific cat breeds. J Feline Med Surg 2006; 8: 1–5.
Google Scholar | SAGE Journals | ISI
8.Riemer, F, Kuehner, KA, Ritz, S. Clinical and laboratory features of cats with feline infectious peritonitis - a retrospective study of 231 confirmed cases (2000–2010). J Feline Med Surg 2016; 18: 348–356.
Google Scholar | SAGE Journals | ISI
9.Rohrbach, BW, Legendre, AM, Baldwin, CA. Epidemiology of feline infectious peritonitis among cats examined at veterinary medical teaching hospitals. J Am Vet Med Assoc 2001; 218: 1111–1115.
Google Scholar | Crossref | Medline | ISI
10.Warren, TK, Jordan, R, Lo, MK. Therapeutic efficacy of the small molecule GS-5734 against Ebola virus in rhesus monkeys. Nature 2016; 531: 381–385.
Google Scholar | Crossref | Medline | ISI
11.Sheahan, TP, Sims, AC, Graham, RL. Broad-spectrum antiviral GS-5734 inhibits both epidemic and zoonotic coronaviruses. Sci Transl Med 2017; 9. DOI: 10.1126 / scitranslmed.aal3653.
Google Scholar | Crossref
12.Murphy, BG, Perron, M, Murakami, E. The nucleoside analog GS-441524 strongly inhibits feline infectious peritonitis (FIP) virus in tissue culture and experimental cat infection studies. Vet Microbiol 2018; 219: 226–233.
Google Scholar | Crossref | Medline
13.Takano, T, Endoh, M, Fukatsu, H. The cholesterol transport inhibitor U18666A inhibits type I feline coronavirus infection. Antiviral Res 2017; 145: 96–102.
Google Scholar | Crossref | Medline
14.Takano, T, Nakano, K, Doki, T. Differential effects of viroporin inhibitors against feline infectious peritonitis virus serotypes I and II. Arch Virol 2015; 160: 1163–1170.
Google Scholar | Crossref | Medline
15.Kim, Y, Liu, H, Galasiti Kankanamalage, AC. Reversal of the progression of fatal coronavirus infection in cats by a broad-spectrum coronavirus protease inhibitor. PLoS Pathog 2016; 12: DOI: 10.1371 / journal.ppat.1005531.
Google Scholar | Crossref
16.Gut, M, Leutenegger, CM, Huder, JB. One-tube fluorogenic reverse transcription-polymerase chain reaction for the quantitation of feline coronaviruses. J Virol Methods 1999; 77: 37–46.
Google Scholar | Crossref | Medline | ISI
17.Agostini, ML, Andres, EL, Sims, AC. Coronavirus susceptibility to the antiviral remdesivir (GS-5734) is mediated by the viral polymerase and the proofreading exoribonuclease. MBio 2018; 9. DOI: 10.1128 / mBio.00221-18.
Google Scholar
18.Weiss, G, Goodnough, LT. Anemia of chronic disease. N Engl J Med 2005; 352: 1011–1023.
Google Scholar | Crossref | Medline | ISI
19.Kurnick, JE, Ward, HP, Pickett, JC. Mechanism of the anemia of chronic disorders: correlation of hematocrit value with albumin, vitamin B12, transferrin, and iron stores. Arch Intern Med 1972; 130: 323–326.
Google Scholar | Crossref | Medline
20.Taylor, SS, Tappin, SW, Dodkin, SJ. Serum protein electrophoresis in 155 cats. J Feline Med Surg 2010; 12: 643–653.
Google Scholar | SAGE Journals | ISI
21.Hirschberger, J, Hartmann, K, Wilhelm, N. Clinical symptoms and diagnosis of feline infectious peritonitis. Tierarztl Prax 1995; 23: 92–99.
Google Scholar | Medline
22.Pedersen, NC, Liu, H, Gandolfi, B. The influence of age and genetics on natural resistance to experimentally induced feline infectious peritonitis. Vet Immunol Immunopathol 2014; 28: 152–154.
Google Scholar
23.Jain, N, Reddy, DH, Verma, SP. Cardiac abnormalities in HIV-positive patients: results from an observational study in India. J Int Assoc Provid AIDS Care 2014; 13: 40–46.
Google Scholar | SAGE Journals
24.Payne, JR, Brodbelt, DC, Luis Fuentes, V. Cardiomyopathy prevalence in 780 apparently healthy cats in rehoming centers (the CatScan study). J Vet Cardiol 2015; 17 Suppl 1: S244 – S257.
Google Scholar | Crossref | Medline

Efficacy of a 3C-like protease inhibitor in treating various forms of acquired feline infectious peritonitis

Original article: Efficacy of a 3C-like protease inhibitor in treating various forms of acquired feline infectious peritonitis
Published: 13.9.2017, SAGE - Journal of Feline Medicine and Surgery

Niels C Pedersen,1 Yunjeong Kim,2 Hongwei Liu,1 Anushka C Galasiti Kankanamalage,3 Chrissy Eckstrand,4 William C Groutas,3 Michael Bannasch,1 Juliana M Meadows,5 and Kyeong-Ok Chang2

Abstract

The goal

The safety and efficacy of the 3C-Like protease inhibitor GC376 was tested in a group of client-owned cats with various forms of infectious peritonitis (FIP).

Methods

Twenty-four cats aged 3.3 to 82 months (mean 10.4 months) with various forms of FIP were enrolled in the clinical trial. Fourteen cats had wet or mixed FIP and six cats had dry FIP. GC376 was administered subcutaneously every 12 hours at a dose of 15 mg / kg. Cats with neurological symptoms were excluded from the study.

The results

Nineteen of the 20 GC376-treated cats recovered within 2 weeks of starting treatment. However, symptoms of the disease returned after 1-7 weeks of primary treatment, and relapses and new cases were finally treated for at least 12 weeks. Relapses that stopped responding to treatment occurred in 13 of these 19 cats within 1-7 weeks of initial or repeated treatment. Severe neurological disease occurred in 8/13 cats that failed treatment, and abdominal lesions recurred in five cats. At the time of writing, seven cats were in remission. Five kittens aged 3.3–4.4 months with wet FIP were treated for 12 weeks and were in remission for 5–14 months (mean 11.2 months) after treatment and at the time of writing. The sixth kitten was in remission for 10 weeks after 12 weeks of treatment, but relapsed and responded well to the second round of GC376 treatment. The seventh was a 6.8-year-old cat with mesenteric lymph node involvement, who managed to achieve remission after three relapses, which required successively longer repeated treatments for 10 months. Treatment side effects included injection burning and occasional foci of subcutaneous fibrosis and hair loss. In cats treated before 16.-18. week, there was a slow development and abnormal growth of permanent teeth.

Conclusions and significance

GC376 has been shown to be promising in the treatment of cats with specific forms of FIP, opening the door to targeted antiviral therapy.

Introduction

Drugs that directly inhibit viral replication have become key supports in the treatment of chronic viral infections such as HIV / AIDS, hepatitis C virus (HCV), hepatitis B virus, herpesvirus and acute infections such as influenza. RNA viruses, such as HIV-1 and HCV, contain ideal targets for inhibiting viruses, such as RNA-dependent RNA polymerase and protease. Proteases are a particularly good target because they are involved in virus maturation (HIV) or in the production of functional viral proteins (HCV). Protease inhibitors are also used in combination with reverse transcription inhibitors in the lifelong treatment of HIV / AIDS. Combinations of different protease inhibitors are highly effective in treating HCV infection in humans. Therefore, it is not surprising that viral protease should also be an attractive target for research into animal infections caused by RNA virus. Kim et al. synthesized peptidyl compounds that target 3C-like (3CLpro) proteases and evaluated their efficacy against feline coronavirus (FCoV) and feline calicivirus, as well as important human RNA viruses that encode 3CLpro or a related 3C protease. They identified a series of compounds that showed strong inhibitory activity against various coronaviruses, including FCoV, with a high safety margin. The efficacy of their 3CLpro inhibitors has been tested in mice infected with hepatitis A59 virus, murine coronavirus, and has been found to cause significant reductions in virus titers and pathological lesions.

There are currently no commercially available antiviral drugs for coronavirus infections in humans or animals, and studies by Kim et al. demonstrated that inhibition of 3CLpro could lead to suppression of coronavirus replication in vivo. They have shown that some of their 3CLpro inhibitors are useful as therapeutic agents against these important viruses in domestic and wild cats. This was confirmed by a study using experimental infection with feline infectious peritonitis virus in laboratory cats. Although experimental FIPV infection is highly fatal, once the infection has reached a definable stage, 14-20 days of GC376 treatment resulted in rapid remission of the disease in six cats, which lasted more than 12 months at the time of publication.

Materials and methods

Official protocols

This study was conducted in accordance with Protocol 18731 approved by the Institutional Committee on the Care and Use of Animals and the Clinical Trials Evaluation Committee of the Veterinary Medical Teaching Hospital at the University of California, Davis. This protocol details the testing conditions for the new protease inhibitor GC376 in client-owned cats. Each owner was required to read and agree to the study conditions.

Organization of a clinical trial

The study evaluated the 3CLpro inhibitor GC376 in a group of cats with naturally acquired FIP. The study did not include a placebo group because, as Miller and Brody noted, “a major ethical principle in placebo-controlled clinical trials is that if there is a proven effective treatment for the condition, testing against a placebo is unethical.” GC376 had already been shown to be highly effective in treating cats with experimentally induced FIP prior to this study, presuming that an effective treatment existed. The placebo control was replaced by a group with naturally occurring disease. None of the 20 treated cats demonstrated continued beneficial responses to the treatment they received prior to GC376 treatment.

The institutional rules precluded the use of cats obtained from shelters or similar research facilities of this type, and required that all cats be legally owned / adopted and treated with the express consent of the owner. Cats with clinically obvious neurological disease were excluded. The study eventually included 20 cats from different areas of the United States, of different ages, and with various forms of FIP. This relatively small group of cats provided valuable insights into the design of the trial, interaction and compliance with the owner, safety and efficacy monitoring, determination of the minimum dosing regimen, evaluation of disease relapses during or after treatment, and determination of clinical forms of FIP that are most appropriate for treatment. This information will hopefully assist in further testing needed for the licensing and possible commercialization of GC376 and for performing similar tests on future antiviral drugs for FIPV and other chronic feline viral infections.

Test group description

Twenty cats and their owners were included in the experiment, and the relevant information for each cat is shown in Table 1 and for the entire experimental group in Figure 1. The cats were enrolled in the study with varying degrees of preliminary testing by primary care veterinarians. This testing usually involved a complete blood count (CBC) with total plasma protein, globulin (G), albumin (A), A: G; serum chemical profile and effusion analysis, including total protein, actual or estimated cell numbers and inflammatory cell type. A small proportion of the cats underwent additional testing, which included FIPV antibody titers, abdominal or thoracic ultrasound, affected tissue biopsies, and real-time quantitative PCR (qRT-PCR) from the effusions.

Table 1
Basic data, origin, main clinical signs and main findings at autopsy after treatment with protease inhibitor GC376

ID / NameAge (months)Weight
(kg)
GenderTribeOriginSymptomsConditionAutopsy
CT01 (Echo)5.61.64FSDSHKRPeritonitis, stunted-B, Int
CT02 (Cate)62.67FSDLHKRPeritonitis, stunted-B, E, Int, L, MLN
CT03 (Pancake)7.863.18MCHimCTDry (Col) to moist+Int, L, MLN, S, Om, P
CT04 (Kratos)824.8MCDSHKRDry (MLN)Remission
CT05 (Scooter)104.25MCDSHKRDry (E, MLN, K)-B, E, L, K, MLN
CT07 (Mac)6.62.6MCDSHKRDry (Col)+E, Int, L, MLN, S, K, A, Lu
CT08 (Phoebe)4.22.18FSDSHKRDry (E)-B, E, K, MLN, S
CT09 (Sammy)10.52.89MCDSHKRDry (MLN, K)?*B*
CT10 (Bandit)17.94.06MCHimCTDry (Col) to moist+B, E, Int, L, MLN, K, Om, P, Lu
CT12 (Daisy)7.52.5FSDSHKRPeritonitis, stunted-B, Int, L, S
CT13 (Leo)7.41.97MCSphynxCTDry (E, K)+B, E, Int, L, MLN, S, K
CT14 (Muffin)82.94FSDSHKRDry (Col) to moist+E, Int, L, MLN, K, Om, P
CT15 (Flora)4.32.39FDSHFCPeritonitisRemission
CT16 (Bean)41.4FSDSHKRPeritonitis, stunted+B,† E, Int, L, MLN, S, Om, P
CT17 (Peanut)4.42.3MDSHKRPeritonitisRemission
CT18 (Smokey)41.84MCDSHKRPeritonitisRemission
CT20 (Cloud)3.31.55MRMCTPleuritis (MLN)Remission
CT21 (Phoebe)4.81.92FDSHKRPeritonitisRemission / relapse / re-treatment
CT22 (Pepper)3.31.6FSiberianCTPeritonitis+B, E, Om, MLN, Lu, Dia
CT23 (Oakely)3.93.1FSDSHKRPeritonitisRemission
Average10.282.59
SD17.220.94
FS = castrated female; F = uncastrated female; DSH = domestic shorthair; KR = rescued kitten; B = brain; Int = intestine; DLH = domestic longhair; E = eye; L = liver; MLN = mesenteric lymph nodes; Him = Himalayan; Col = colon; S = spleen; Om = omentum; P = peritoneum; MC = castrated male; M = uncastrated male; K = kidney; A = adrenal gland; Lu = lungs; FC = cat colony; RM = ragmuffin; Dia = diaphragm, SD = Standard deviation; CT = Kennel

* No autopsy was performed, but terminal neurological symptoms were present
† Severe cerebral edema, no typical inflammatory lesions have been reported

Figure 1.
Demographics of study cats. (a-c) Pie charts summarizing the percentage of patients: (a) age in months, (b) breed, or (c) origin. (d) Bar graph showing forms of feline infectious peritonitis (FIP) enrolled patients.
M = months; DSH = domestic shorthair; DLH = domestic longhair; MD = Maryland; OH = Ohio; Tx = Texas; FL = Florida; IL = Illinois; CT = Connecticut; CA = California

Cats with clinical signs of neurological impairment were excluded from the study based on previous unpublished experimental studies with GC376. One cat that survived a previous study of the pharmacokinetics and efficacy of GC376 had a recurrence of FIP with neurological symptoms 6 months after appearing to be a successful treatment for acute infection.6 This cat did not respond to a repeated GC376 penetration study that prompted a penetration study. to the brain. GC376 levels in laboratory cat brain represented only 3% plasma drug concentrations.

Confirmation of the disease

The diagnosis of FIP was confirmed at study entry based on baseline data, clinical history, examination of previous laboratory tests, physical examination, and repetition of baseline blood and effusion tests. Manual abdominal palpation was usually sufficient to identify ascites, enlarged mesenteric lymph nodes, appendix enlargement and associated ileocecal-colic lymph nodes, renal tumors, and colonic infiltration. Manual palpation was supplemented with ultrasound if necessary. The eyes were initially examined with direct light for any abnormalities in the retina, for clots in the anterior chamber or on the back of the cornea, and flashes in the ventricular water. The presence of ocular disease was confirmed by a complete ophthalmoscopic examination performed by the Ophthalmological Service of the Veterinary Medical University Hospital (VMTH), UC Davis. The presence of FIPV was further confirmed by qRT-PCR, either from abdominal or thoracic effusions collected at the time of admission or at the time of necropsy. Sequencing of the FIPV protease gene was performed on cats that relapsed during treatment to determine if there was a potential mutation causing drug resistance.

The diagnosis of dry-wet (mixed) FIP in three cats (CT03, CT10 and CT14) was based on diffuse colon enlargement and a history of loose stools, blood and mucus in the stools, defecation strains and small caliber stools before abdominal effusions. Colon FIP has been described as a specific variant form of non-fusive FIP. Mixed FIP was also suspected in cats CT01, CT02 and CT12 due to growth arrest, which preceded the occurrence of abdominal effusions by many weeks.

Treatment regimen

GC376 was synthesized in highly pure form and prepared at a concentration of 53 mg / ml in 10% ethanol and 90% polyethylene glycol 400 as described above. GC376 was administered subcutaneously (SC) at a dose of 15 mg / kg every 12 hours of SC, unless otherwise stated. The effective dose for cats with experimentally induced FIP was 10 mg / kg / q12 h SC, but the dose was increased to 15 mg / kg after the first cat (CT01) did not respond to the lower 10 mg / kg dose determined by previous pharmacokinetic studies. It was a clinical decision based on this cat's response to treatment.

Monitoring response to treatment
Based on preliminary testing and initial evaluation at the time of presentation at UC Davis, cats with FIP were hospitalized for at least 5 days and started treatment immediately. They were examined in detail for rectal temperature, pulse, respiration, appetite and activity at least twice a day. A clumping litter was used to allow daily evaluation of stool volume and consistency and urination. Whole blood was collected into EDTA or heparin by venipuncture before treatment, at two-day intervals during hospitalization, at discharge time, and at two-week intervals during the first month and at monthly or longer intervals thereafter. Routine blood tests at each time point included minimal hematocrit, total plasma protein, icteric index, total white blood cell count, differential white blood cell count, and absolute neutrophil, lymphocyte, and monocyte and eosinophil counts. To check the potential toxicity of the medicines, blood serum chemistry values were recorded regularly. Abdominal effusion samples were obtained by paracentesis every other day if they could be obtained, which was usually the first 3-7 days. Cats with shortness of breath were examined by thoracic ultrasonography and a fluid sample was obtained by ultrasound-guided paracentesis. The effluents were examined for the presence of fibrin clots, neutrophil and small / large mononuclear cell admixtures, yellowing intensity, fiber viscosity, and total protein content. Cell pellets from peritoneal or thoracic effusions were also examined by qRT-PCR for viral RNA levels as previously described.

Cats were issued to their owners when a positive response to treatment was noted, usually within 5 days. The owner (s) were instructed by either the chief veterinarian or the primary care veterinarian how to administer the drug twice daily by subcutaneous injection. The injection sites were varied to include the upper line from the nape of the neck to the middle of the back and to the sides of the chest and hips. Care was taken to avoid storing the drug in the dermis or gradually in the same subcutaneous site. Owners were encouraged to maintain daily records of rectal temperature, activity, appetite, defecation and urination, and weekly to biweekly body weights. Periodic blood samples for CBC and serum chemistry were collected by the owners' personal veterinarians and sent to commercial veterinary diagnostic laboratories. Any abnormal symptoms or behavior should be noted and reported immediately. Euthanasia was performed at either UC Davis or a primary care veterinarian, as appropriate. The bodies of the cats killed by the primary care veterinarians were immediately cooled and sent in ice packs by express mail to UC Davis for autopsy. The owners' requirements for treatment and final disposition of the body were respected.

The results

Determination of treatment duration

The first five cats in the study were initially treated for 2 weeks (CT01, CT02, CT03, CT04 and CT05). A rapid improvement in health was observed in all cats and treatment was discontinued. Despite a favorable initial response, symptoms of the disease were repeated 1 (CT01, CT05), 2 (CT03, CT04) or 7 (CT02) weeks after the end of the 2-week treatment (Figure 2). The cats were then treated again, due to a gradual prolongation of the primary and secondary treatment time until their FIP remained sensitive to GC376 (see CT04, CT22, Figure 2). New cats that entered the study were further treated for 3 (CT07) or 4 weeks (CT08, CT16). Cats CT08 and CT16 initially responded, but their symptoms reappeared during treatment. Cat CT08 developed neurological disease, while cat CT16 had recurrent abdominal lesions (Table 1). Primary and secondary treatment times were then extended to 9 weeks (CT07, CT09, CT10, CT14) (Figure 2). Cat CT09 developed neurological symptoms during the 9-week basic treatment and was eventually sacrificed when the symptoms of the disease became severe. CT07 developed neurological disease 6 weeks after the start of the second treatment. From this point, all new cats were accepted into the study and older cats, such as CT10, were treated or re-treated for at least 12 weeks. The benefit of 12 weeks of treatment was most evident in the CT04 cat, which had previously been treated three times with a shorter treatment period followed by relapse (Figure 2). Treatment was discontinued in cats that had no clinical or laboratory signs of disease after 12 weeks of primary or secondary treatment. It was found that the minimum treatment period should be around 12 weeks. Cat CT21 was treated for 17 weeks due to delayed improvement in total protein and white blood cell counts (Figure 2). This cat relapsed pleural FIP 13 weeks later and underwent further treatment at the time of writing.

Figure 2.
Treatment time scale and clinical outcome of 20 cats that entered the clinical study with the protease inhibitor GC376. The periods during which the cats were treated are indicated by solid lines. The date of the last day of treatment is given for six cats that have achieved permanent clinical remission. Cat 21 was still in treatment at the time of writing. The remaining 13 cats succumbed to non-neurological FIP or neurological FIP after completion of primary or secondary treatment within 0-7 weeks.

Response to initial treatment and indicators of favorable response

During the first 1-4 weeks of treatment, 19/20 cats showed a dramatic and progressive improvement in health. The exception was the CT16 cat, which responded by a drop in rectal temperature during the first 4 days of treatment. However, the fever returned and the health continued to deteriorate over the next 23 days and the cat was euthanized. The fever (> 38.9 ° C) in the other 19 cats disappeared within 24-48 hours, with an improvement in appetite, activity, growth and weight gain. Abdominal effusions were usually undetectable within 2 weeks. The residual thoracic effusion remaining after the initial therapeutic drainage after 3 days in the CT20 cat almost disappeared. Renal tumors in cats CT02 and CT13 also shrunk rapidly and were no longer palpable after 2 weeks. Enlarged mesenteric lymph nodes returned to normal size more slowly. The palpable colon thickening and associated ileo-cecal-colic formations responded the slowest and persisted in the CT03 cat despite treatment and a return to an otherwise normal state of health. Jaundice, a common finding in younger cats with effusive FIP, slowly resolved over 2 weeks or more, with a reduction in hyperbilirubinemia. Symptoms of ocular disease began to resolve within 48 hours and resolved within 1 week, regardless of initial severity (Figure 3).

Figure 3.
Appearance of CT08 cat eyes before treatment (a) and one week later (b). This cat developed severe neurological symptoms 3 weeks after the start of treatment.

Weight gain was a simple and accurate criterion for growth and health improvement. The weight of cat CT04, the oldest cat in the test, was used as a reference value for this parameter (Figure 4a). Cat CT04 showed a significant weight loss of 30%. She gained weight after each round of treatment, began to lose weight shortly before each relapse, and gained weight again after each treatment. After 9.3 months without treatment and after treatment (4.8 kg to 7.19 kg), she regained all her lost weight. All kittens with permanent remission during and after antiviral treatment gained weight continuously, indicating that normal growth continued with antiviral treatment (Figure 4b). One cat (CT15) and two cats (CT17, 20) were castrated without complications during disease remission.

Figure 4.
Antiviral treatment and weight changes. (a) Cat CT04, a 6.8-year-old castrated male who had dry feline infectious peritonitis (FIP), underwent four cycles of antiviral treatment with increasing duration, as shown by the dotted boxes. He lost weight before each relapse and gained weight after subsequent treatment. (b) Weight gains in four kittens aged 3.5-4.4 months during and after antiviral treatment are indicated by dots. The dotted rectangle indicates the length of antiviral treatment (12 weeks)

Lymphopenia was a common clinical symptom in cats with wet FIP (Figure 5) and tended to directly correlate with the severity of abdominal inflammation, as indicated by viscosity, presence of fibrin fibers, protein content, cell number, and yellowness of the effusion. Lymphopenia improved in the treatment of all cats with wet FIP except CT16, but did not help predict disease relapses that occurred afterwards (Figure 5a). In cats with dry FIP, lymphopenia was not as severe and was not as useful as other parameters in assessing response to treatment (Figure 5b).

Figure 5.
Mean and standard deviation (SD) of absolute lymphocyte counts in treated patients with (a) wet or (b) dry feline infectious peritonitis (FIP). (a) Twelve cats (empty ring) showing abdominal or thoracic effusion and treated for up to 12 weeks. The thirteenth cat (CT16, full ring) with abdominal effusion responded poorly to treatment. b) Seven cats with dry or wet form of FIP and subsequent treatment for 6 weeks.

Total plasma protein levels as an indirect indicator of globulin concentration were often increased on examination, but values were highly variable during the first 4 weeks and often increased transiently during effusion resorption. Cats that ultimately failed treatment tended to have higher total plasma protein concentrations at the start of treatment and tended to maintain higher levels during treatment than cats that successfully achieved permanent remission (Figure 6).

Figure 6.
Mean and SD of total plasma protein levels in 20 cats over a 12 week period. Thirteen cats suffered fatal relapses at different weeks of treatment (W) and seven cats achieved permanent remission after 12 weeks of treatment (W-SV)

Decreased viral RNA levels in ascitic fluid cells in association with treatment

Sequential ascites samples were taken from several identical cats during the first 6-25 days of antiviral treatment and tested for viral RNA levels by qRT-PCR. FIPV levels are often low or negative in the blood of cats with FIP and are highest in effusion cells. Therefore, cells from ascites or pleural effusions were the most reliable source of FIPV RNA. Cats CT15, CT16 and CT17 had 955, 1699 and 2937-fold higher levels of viral RNA, respectively, than CT02, which had the lowest viral load in pre-treatment effusion (Figure 7). Viral RNA levels decreased up to 1567463-fold over 2 weeks compared to pre-treatment values, except for the CT16 cat (Figure 8), which had the second highest pre-treatment viral RNA level among the 12 cats with effusion samples available for testing (Figure 7). The absence of a rapid decrease in viral RNA levels in the CT16 cat, together with severe lymphopenia, may explain why it did not respond to treatment. CT10 also had a slightly slower decrease in virus levels and relapsed twice after antiviral treatment. Notably, viral RNA levels in ascites cells in CT15, CT17, and CT18 cats declined most rapidly and were also among the five cats that experienced permanent remission of the disease. Whether the cause was a property of individual FIPV isolates or the form and severity of the host disease was not determined.

Figure 7.
Relative initial levels of feline infectious peritonitis virus (FIPV) RNA in patient effusions prior to antiviral therapy. Real-time quantitative PCR was performed on pre-treatment effusion patient samples. Relative baseline viral RNA levels as fold differences compared to viral levels before treatment with CT02, the cat with the lowest RNA levels. RNA transcript levels were calculated for each patient using the ∆Ct method with the beta-actin reference gene
Figure 8.
Reduction of feline infectious peritonitis virus RNA from sequential effusion samples during GC376 treatment in cats CT10, CT12, CT15, CT16, CT17, CT18 and CT23. Each point indicates a fold reduction in viral RNA levels compared to pre-treatment levels (day 0). Viral RNA levels were determined by real-time quantitative PCR using the ∆Ct method and beta-actin reference gene

Treatment failure due to recurrence of abdominal FIP or the occurrence of neurological disease

Thirteen of the 20 cats in the test eventually relapsed. One cat (CT16) did not show significant improvement and was euthanized 3 weeks after the start of the 4-week treatment regimen (Figures 2 and 8), 8), while the other 12 had a variable period of disease remission after primary or secondary treatment lasting 3-17. weeks (mean 7.8 weeks) (Figure 2). All but one of these 13 cats (CT09) were necropsied (Table 1). Eight of these cats were euthanized for severe neurological symptoms and five for recurrent abdominal disease (Figure 2). Three cats that underwent neurological disease (CT05, CT08, CT13) due to ocular FIP were secondary to the examination (Table 1). The earliest symptoms of neurological disease included fever, which persisted despite continued treatment, apathy, occasional muscle twitching of the ears and muscles, unusual swallowing movements, compulsive limb twitching, and loss of normal mentality, manifested by brief episodes of numbness or numbness. These symptoms persisted during treatment for several days or weeks, but eventually led to incoordination and tonic / clonic seizures. The incidence and rapid progression of neurological symptoms after discontinuation of treatment were more pronounced than during treatment (Figure 2).

Five cats (CT03, CT07, CT10, CT14 and CT16) had a recurrence of typical intra-abdominal lesions in the absence of neurological symptoms during or after treatment (Table 1). Four of them had ileocecal formations (CT03, CT07 and CT14) or an enlarged colonic lymph node (CT10) that had shrunk (CT03, CT10 and CT14) or were no longer palpable (CT07) after primary treatment. However, CT03 continued to suffer from severe constipation, strain, and toothpaste-like stools. The severity of colonic obstruction required resection of the colon, which alleviated clinical symptoms but did not prevent a recurrence of abdominal disease. All three cats that developed severe ileocecal infiltrates still showed evidence of this form of FIP at necropsy, and immunohistochemistry showed FIPV antigen in macrophages in granulomatous inflammation (Figure 9).

Figure 9.
An incision from the severely thickened wall of the resected colon from cat CT03. Immunoperoxidase (brown) stained for feline antigen of infectious peritonitis virus is observed in macrophages around the periphery of the granulomatous lesion. Persistence of the virus in the colon occurred during treatment and remission of other symptoms of the disease (eg effusive peritonitis)

Attempts to treat a neurological disease by increasing the dose of the drug and prolonging the duration of treatment

To alleviate neurological symptoms, we tried to increase the dose of GC376, thereby increasing its blood level and the amount of drug that crossed the blood-brain barrier. Cat CT01 showed effusion FIP and was initially treated with GC376 (10 mg / kg q12h SC for 9 days). The cat responded well, but on day 9 the fever returned and the dose was increased to 15 mg / kg every 12 hours for 5 days. The fever disappeared and treatment was stopped on day 14. Three days later, the fever returned along with indeterminate neurological symptoms consisting of muscle twitching, abnormal limb stretching, and abnormal swallowing movements. The cat was immediately re-administered a dose of 15 mg / kg every 12 hours of SC and its condition improved, but soon after it worsened with the return of fever and the same vague neurological symptoms with mild incoordination. The dose was then increased to 50 mg / kg every 12 hours of SC for 14 days and improved to near normal. Treatment was stopped, but neurological symptoms returned immediately. The cat was then treated for another four days with a dose of 50 mg / kg q12 h SC, during which the neurological symptoms improved again. However, the decision was made to stop the treatment completely. The cat's condition remained stable for 1 week and then developed extreme incoordination, dementia and tonic / clonic seizures. Euthanasia was performed and autopsy showed lesions only in the brain.

Cat CT12 responded well to treatment at 15 mg / kg q12 h SC; rectal temperature returned to normal within 48 hours and abdominal effusion disappeared within 2 weeks. The cat appeared normal after the second week of treatment, but then had a persistent fever of 38.9-40 ° C. The owners felt that the cat otherwise had normal activity and appetite, so the treatment continued at the same dosage. However, the fever persisted, mild signs of behavior change were observed, and the cat did not grow as expected. The cat continued treatment for another 15 weeks, during which the drug dose was temporarily reduced twice (ie to 10 mg / kg every 12 hours and 15 mg / kg every 24 hours) for several days, but the fever increased and the activity decreased each time. Dosing of 15 mg / kg was resumed every 12 hours. The cat continued to show signs of variable fever and unclear signs of behavior, but the owners were optimistic about the cat's appetite and activity level. The treatment of the cat was then stopped because further use of the drug for this purpose could not be justified. The cat's condition remained unchanged with persistent fever, solitary behavior and stunted growth for another 5 weeks. At week 22, severe neurological symptoms consisting of incoordination, dementia and seizures appeared and the cat was euthanized. Macroscopic and microscopic lesions were limited to the brain.

Viral resistance testing

The development of a drug-resistant virus was considered in the CT03 cat, which relapsed with abdominal lesions after an initial favorable response to the treatment of granulomatous colitis and mixed FIP. At the time of necropsy, granulomatous lesions were still present in the abdominal cavity and no macroscopic or microscopic lesions were found in the brain (Table 1). Therefore, disease recurrence was not associated with neurological disease and FIPV persistent antigen was identified in macrophages in granulomatous lesions. Sequence comparisons were made between 3CLpro from pre-treatment effusion and from the omentum taken at autopsy 95 days later. However, no amino acid substitutions were found in 3CLpro, suggesting that the presence of drug-resistant virus was not the cause of recurrent cat disease.

Pre-treatment 3CLpro viral RNA sequences were also compared with those obtained 25 days (CT16), 139 days (CT02), 149 days (CT12) and 231 days (CT10) later at necropsy. No differences in 3CLpro were observed during this period. The sequences also remained unchanged for CT02, CT16 and CT12 from the time of admission to necropsy. CT10 lung and spleen viral 3CLpro, which relapsed twice for 8 months and was re-treated, showed an Asp-to-Ser substitution at position 25 and a Lys-to-Asp substitution at position 260 compared to the pre-treatment abdominal fluid virus. . The exact effects of these mutations on protease function are currently being investigated. Genetic evolution of quasi-viral proteins has been reported to occur over time in patients chronically infected with RNA virus (HCV) and may lead to sporadic amino acid changes.

Occurrence of permanent clinical remissions

Seven of the 20 cats in the GC376 treatment study, all of whom underwent at least 12 weeks of continuous treatment, were categorized as potential treatment successes based on more than 12 weeks of disease remission after cessation of treatment (Figure 2). Six of these kittens had an acute abdominal effusion (CT15, CT17, CT18, CT21, CT23) or pleural (CT20) disease at 3.3-4.4 months of age and were treated continuously for 12 or 17 (CT21 cat) weeks (Table 1, figure 2). The seventh cat (CT04), a 6.8-year-old cross-castrated male with dry FIP restricted to the mesenteric lymph node, also achieved long-term remission, but only after four treatment cycles of increasing duration (Table 1, Figure 2).

Six of these long-lived cats had abnormalities in CBC, hematocrit, and total proteins at the start of treatment, but had completely normal blood levels at the time of treatment. However, the CT21 cat still had elevated plasma protein levels and an increased white blood cell count after 12 weeks and continued treatment for another 5 weeks. Plasma protein and white blood cell counts improved after another 5 weeks of treatment, but were still not within the reference range. Thirteen weeks after the end of treatment, the cat developed a typical FIP chest effusion with fever. Chest fluid was aspirated to improve respiration, and the cat began a second round of GC376 and at the time of writing was afebrile, active, and ate after 8 weeks of treatment. The treatment will last for 12 weeks if there are no signs of the disease again.

Side effects observed during and after treatment

Two side effects were observed during and after GC376 treatment. The drug often caused stinging / burning when injected. Subcutaneous edema occurred when too many injections were given at the same site, but they resolved rapidly. One cat (CT12) experienced deeply localized ulceration between the scapulae at approximately week 14 of the 18-week treatment period. However, no evidence of dermal FIP was observed at necropsy and was likely a response to continuous injections at the same site. A survey of seven long-lived cats showed appreciable focal subcutaneous thickening. In one cat, four calcified peas the size of peas appeared on X-rays. These lumps were surgically removed along with the surrounding fibrotic tissue. The other three long-term survivors have 1-3 small focal areas with permanent hair loss at the injection sites, which are covered by the surrounding fur (Figure 10). The owners and their veterinarians were asked to check these lesions regularly for any changes or the appearance of new lesions.

Figure 10.
Focal area of permanent hair loss caused by unwanted deposition of GC376 in the epidermis of cat CT21. These areas were usually covered with hair and were not visible from the outside

The most significant side effect associated with long-term treatment was juvenile teeth. Normal formation, growth and incision of permanent teeth were delayed in all four treated kittens aged 3.3-4.4 months. The ocular teeth, incisors, fourth premolar and molar were the least affected, while the second and third premolar were the most affected (Figure 11). Adult teeth appeared smaller than normlingual, and this, together with the delayed cutting, led either to the retention of the deciduous canines, the failure of the deciduous teeth or the partial incision of the abnormal permanent teeth to the concurrent deciduous teeth. No other anatomical or physiological defects were observed in any of the long-term survivors and no autopsy was observed.

Figure 11.
Adult teeth of a CT17 cat who was treated with GC376 for 12 weeks, starting at 4.4 months of age. The upper left milk canine is visible. The upper second and third premolars appear to be milky. The small permanent third premolars were partially cut lingually to the dairy third upper premolars. The gingiva surrounding the left canine and premolars is inflamed. Adult canines also appear smaller than usual. The permanent right canine and fourth upper premolar appear to have cut normally

Autopsy findings

The bodies of 12/13 cats that did not succeed in treatment were necropsied, including a rough and histological examination and immunohistochemistry of the affected tissues for FIPV antigen. Tissues collected and examined included representative sections of all major abdominal and thoracic organs, brain and eyes. The rough examination identified three different presentations. Five cats did not show significant signs of active FIP (CT01, CT02, CT05, CT08, C12), three had lesions corresponding to non-fusion FIP (CT07, CT10, CT13) and four had effusion peritonitis with multiorgan involvement (CT03, CT14, CT16, CT22). The histology of the five cats, which did not show sufficient evidence of the disease, showed mostly mild mononuclear infiltrates, usually perivascular inflammation in the eye, liver, intestinal wall and kidneys. Three cats with non-fusion FIP had mild to severe inflammation in many organs with the most severe lesions in the eye, mesenteric lymph nodes, kidneys, and lungs. Three cats with effusion FIP had severe pyogranulomatous inflammation in several abdominal organs, including the omentum, peritoneum, intestinal wall, mesenteric lymph nodes, liver, and spleen.

Severe inflammation typical of cerebral FIP was present in the brains of all but one (CT07) of the eight cats that underwent necropsy without significant signs of FIP or with non-fusion FIP. One cat without characteristic brain lesions had severe cerebral edema. In contrast, typical FIP lesions were absent in the brains of all three dissected cats with effusive FIP. Stereotypic FIP brain lesions were characterized by moderate to severe chronic meningoencephalitis and ventriculitis associated with periventricular necrosis of the parenchyma (Figure 12a). The fourth ventricle was the most severely affected, and meningitis was most often observed ventrally into the cerebellum and brainstem. Strong perivascular cuffs associated with vasculitis have often been observed. FIP antigen was demonstrated by immunoperoxidase staining in the brain of 6/7 cases of stereotyped cerebral FIP (Figure 12b). Tissues from 11 dissected cats were tested for the presence of FIPV RNA by qRT-PCR. All showed a positive result, thus determining the persistence of the virus in cats in which treatment was not successful.

Figure 12.
Photomicrographs of lesions in cat brain CT08. This cat developed a severe neurological disease during the initial treatment of GC376. (a) The fourth chamber contains protein fluid mixed with numerous neutrophils and macrophages that interfere multifocally with the surrounding dilute neuropil. Large cuffs of lymphocytes and plasma cells surround blood vessels (*) (hematoxylin staining, 20x magnification). (b) Several cells resembling peritoneal macrophages (marked small area in Figure 12a) show positive immunoreactivity for feline infectious peritonitis antigen (hematoxylin contrast dye, 600x magnification).

Discussion

Success in the treatment of GC376 in experimental FIPV infection motivated us to examine the efficacy of GC376 in naturally developed FIP. There are significant differences between experimental fusion abdominal FIP and naturally occurring disease. The experimental disease bypasses the critical initial stage, which begins in kittens by exposure to the harmless feline enteric coronavirus (FECV). Naturally occurring FIP is the result of specific mutants that arise after FECV infection, and FIP occurs in the presence of immunity to FECV. In contrast, experimental FIP is induced in cats that have not encountered coronavirus by intraperitoneal injection of a large dose of purified FIPV obtained from a laboratory cat. The naturally occurring disease is often subclinical for many weeks or months before observing external signs of the disease, while experimental symptoms of the disease appear within 2-4 weeks and progress rapidly. Naturally occurring FIP has various clinical forms, while experimental infection almost always has an abdominal effusion form. FIP in nature is also affected by the environment of disease-increasing cofactors, while experimental disease occurs in cats without external influences. Differences may explain why only a small proportion of cats naturally exposed to FIPV develop the disease, while 80-100% experimentally infected cats die. Our predictions proved to be correct, and naturally occurring FIP was much more difficult to treat than experimental disease. However, it should be emphasized that this experiment would not have been approved without the information obtained from pharmacokinetic studies, acute and chronic toxicity and efficacy studies performed in laboratory cats.

It was the first attempt to use a targeted antiviral drug against a systemic and highly fatal veterinary disease. Although no specific antiviral drugs for coronavirus infections in humans or animals are yet available, antiviral drugs for other human viral infections, such as HCV and HIV-1, have been developed for treatment and the use of these drugs has provided a solid basis for their application to animal diseases such as FIP. HCV mainly infects liver cells and causes a persistent viral infection in most people. However, only about 20-30% of them develop liver disease within a time horizon of 20-30 years. HCV infection can be eliminated by non-specific antiviral therapy (interferon and ribavirin) for 6-12 months in approximately half of the patients, and the recent introduction of direct-acting antiviral drugs for 3-6 months significantly increased the cure rate to more than 90% during treatment. HIV infection in humans leads to a prolonged asymptomatic condition and eventually to advanced HIV disease. HIV-1 infects T cells and macrophages and survives in a latent state. More than 30 antiretroviral drugs, most of which are used in combination with two or more drugs, have been used successfully to reduce the viral load to undetectable levels in the blood of HIV / AIDS patients. However, the virus returns after discontinuation of antiviral treatment and thus requires lifelong antiviral treatment. The spread of the virus to the brain, which is mainly mediated by virus-infected macrophages, and the subsequent development of neurological disease occur in more than 50% HIV infections. Therefore, neurological deterioration still remains an important problem at this time of antiviral treatment. These precedents for antiviral treatment of HCV and HIV-1 infections indicate that treatment outcome (viral clearance vs. viral persistence), duration of treatment (final vs. continuous) and the presence of neurological sequelae are strongly influenced by viral pathogenesis.

This study was limited to 20 cats with FIP, which represented the spectrum of age and forms of the disease. Although the number of cats treated was small, a surprising amount of information was gathered, such as how long to be treated, possible side effects, how to identify the clinical form of FIP that is most likely to respond to treatment, and potential indicators. treatment failure and its success. The clinical study was based on experience gained from pharmacokinetic and efficacy studies performed in laboratory cats. Based on experimental studies, the initial treatment period was set at 2 weeks, but was eventually extended to 12 weeks or more based on experience gained during testing. This final treatment period was close to 3-6 months used to treat HCV infection in people with direct-acting antiviral drugs. Based on experimental studies, difficulties in treating neurological forms of the disease have been expected. Side effects were acceptable and included injection burning and dermal and subcutaneous inflammation when too much drug was administered to the same sites. This phenomenon has previously been observed in laboratory cats. A more serious side effect not previously observed in laboratory cats was limited to kittens and included slowed development of adult teeth and retention or delayed loss of deciduous teeth.

GC376 treatment was successful in inducing significant remission of disease symptoms and regression of lesions in 19/20 cats. This result confirms our findings of a rapid reversal of clinical signs in laboratory cats with experimental FIP treated with GC376, and expanded our knowledge of the effects of the drug on a wide range of forms of naturally occurring FIP. The cats came from different parts of the United States and even Peru, confirming that the geographically diverse strains of FIPV were equally sensitive to this inhibitor. Significant reductions in viral RNA transcripts in effusions occurred within a few days of treatment, along with a rapid improvement in health. However, remission of the disease persisted for 3 months and longer in only 7/20 of these cats. The inability to achieve long-term remission of the disease was ultimately associated with the occurrence of neurological disease in the absence of extensive abdominal lesions or with recurrence / persistence of extensive abdominal lesions in the presence of histological lesions in the brain and / or eyes. These findings suggest that FIPV has a greater tendency to spread from body cavities to the brain than previously thought, especially if given sufficient time. This spread most likely involves infected macrophages that enter the brain through small blood vessels in the meninges and ependyma.

In cats that developed neurological disease, this occurred either during treatment (CT05, CT08, CT22), or 2 (CT01, CT02, CT09), 3 (CT13) or 6 (CT10) weeks after treatment. The most likely explanation for this delay, as well as some therapeutic benefit of higher doses, was that part of GC376 was still able to penetrate the brain. GC376 levels in cerebrospinal fluid represented only 3% plasma in the brain 2 hours after subcutaneous injection at a dose of 10 mg / kg (unpublished data). Although the relative concentrations of drug in the brain of these cats were low, they were still 21.4 times higher than the levels required to inhibit virus replication in tissue culture. Based on this finding, it was hypothesized that higher doses would allow higher amounts of drug to enter the brain. This assumption was supported by the experience of two cats that showed neurological symptoms. Increasing the dose of GC376 to 50 mg / kg every 12 hours in one cat (CT01) resulted in a marked improvement but did not eliminate the symptoms of brain disease. Prolongation of treatment by almost 3 months at 15 mg / kg every 12 hours appeared to delay the progression of neurological symptoms in the second cat (CT12), while attempts to reduce the total daily dose in this cat to 10 mg / kg every 12 hours or 15 mg / kg caused worsening of neurological symptoms every 24 hours. This suggests that doses of 15 mg / kg every 12 hours or higher allowed sufficient GC376 to cross the blood-brain barrier to slow but not eliminate neurological symptoms.

The high incidence of central nervous system (CNS) disease in this study was higher than previously reported and was unexpected because cats with signs of brain or spinal cord involvement were excluded from the study. CNS diseases have been shown to be much more likely in older cats with dry or mixed FIP than in young cats with wet FIP. This suggests that FIPV can enter the brain of many cats if given sufficient time. Peritoneal-type macrophages appear to play a role in CNS infection because FIPV-infected cells in the brain of cats with neurological FIP are more similar to peritoneal macrophages than to resident brain macrophages. This should come as no surprise, as macrophages migrate to a variety of tissues, including the brain, to perform immune surveillance and are also targets for a variety of infectious agents, such as FIPV and HIV-1. Infected macrophages play a major role in the spread of the virus to the brain in HIV patients, and detection of the virus in the brain is possible within a few weeks of infection. However, neurological damage usually occurs at a later stage. Anti-HIV drugs also reduce the frequency of severe neurological disorders, similar to that observed in this study on FIPV and GC376. There are also alternative explanations. It is possible that extra-CNS involvement may inhibit the development of brain diseases and vice versa. It is common for CNS disease to occur in the absence of visceral disease and vice versa. Suppression of virus replication in non-neuronal tissues may also increase the positive selection of mutants that are more neurotropic or neurovirulent. However, evidence of the latter would require large studies using laboratory cats.

Certain forms of FIP appeared to affect treatment success. The behavior of GC376 in the treatment of ocular FIP was paradoxical because this form responded extremely well to GC376. Although the eye lesions responded to treatment, all three cats with the eye eventually succumbed to brain diseases, which supported a close anatomical relationship between the eye and the CNS. Chronic ileocecal and colon involvement and growth retardation in older cats in this study were also a poor prognosis. In many of these cats, abdominal effusion appeared only as a terminal manifestation of their disease. Host factors also associated with a reduced response to antiviral therapy for other viral infections, such as HCV, include age, gender, cirrhosis or liver fibrosis, race, or body weight.

The development of resistance is a major problem for any antiviral drug, but FIPV is rarely transmitted from cat to cat, and drug resistance, if it occurs, would be a problem only for individual treated cats and not for the entire population. Although viral resistance to GC376 has not been observed for up to 20 passages in vitro, suggesting that resistance cannot be easily acquired, long-term and repeated in vivo treatment may be a stronger selection factor. However, viral resistance did not appear to be responsible for relapses of abdominal disease in the five cats treated. These cats had granulomatous formations, often in the colon and ileo-cecal-colic lymph nodes, which could provide a protected site for viruses to persist. The protection of pathogens in granulomas is a well-documented phenomenon for mycobacteria and applies to other pathogens such as viruses. Liver disease (cirrhosis) from HCV infection also increases the risk of relapse and requires longer treatment, which also suggests that viruses may be protected from drugs when they are in certain protected areas. The formation of "protective granulomas" involves a large number of chemokines and cytokines and upregulation of chemokine receptors, addressins, selectins and integrins. The persistence of pathogens in these sheltered sites may require a higher dose of the drug and a longer duration of treatment.

Treatment failures may also be the result of the host's inability to elicit a protective immune response during periods of viral replication. Such failure has been observed in HCV infection in humans. T-cell mediated immunity plays an important role in the protective immunity that occurs in about 20% acute HCV infection and in the same or greater proportion of FIPV infection. The possible synergies between T-cell-mediated viral clearance and antiviral therapy in cats with FIP have yet to be investigated. A combination of antiviral drugs and T-cell immune stimulants in the treatment of FIP, such as the combination of interferons and ribavirin in the treatment of HCV infection, could also be beneficial.

Sustained remission in 6/7 cats treated for 12 weeks or longer was to some extent predictable. These cats were 3.3-4.4 months old at the time of acute abdominal symptoms (C15, C17, C18, CT21, CT23) or thoracic effusion FIP (CT20). This made them younger than all but three other cats in the study (CT8, CT16, CT21) and more resembled 16-week-old laboratory cats with acute onset effusion FIP, which responded well to GC376. The disease, if acute, gives the virus little time to penetrate the brain or eyes. The acute nature of their disease may also have allowed the infection to permanently disrupt any protective immune response. The seventh cat, CT04, was extreme compared to these six younger cats. At age 6.8, CT04 was the oldest cat in a study that experienced significant weight loss (30%) and mesenteric lymph node disease. CT04 suffered relapses of the disease requiring re-treatment, but all relapses were identical to baseline and did not involve the CNS. Cats with this form of FIP are known to undergo spontaneous remission, suggesting that there is a tipping point between immunity and disease. Cats CT04 and CT21 demonstrated the wise decision to restart treatment in relapse, provided that the relapses did not involve the eyes or nervous system and still respond to drugs.

The determination of the minimum duration of treatment was based on a gradual prolongation of the duration of treatment based on a favorable response to treatment. Based on experimental studies, 2 weeks of treatment were expected to be sufficient; it was therefore used as a starting point. However, this study indicated that the minimum treatment period was close to 12 weeks, which was surprisingly close to the usual 12-week period required to treat people with HCV with protease inhibitors. However, the duration of HCV treatment can range from 8 to 24 weeks in different people. The CT21 cat was healthy, active on the outside and grew after 12 weeks of treatment, but the total protein and white blood cell counts still did not return to normal, as in the other six cats. Nevertheless, it was decided to discontinue treatment after 17 weeks due to the long period of normal health. Whether longer-term treatment could prevent a relapse of the disease 13 weeks after the end of treatment, we can only imagine, but it raises doubts about how long the treatment period should be for some cats. The question also arises as to how long the remission period must be in order for us to declare that there has been a recovery, and not just a long-term remission. The longest disease-free period at the time of writing was more than 11 months, with five additional cats showing no signs of infection for 5-9 months. Based on clinical and histological evidence of neurological disease at the time of fatal relapses, it appears that the virus eventually reaches the brain and may be the most important limiting factor in FIP antiviral therapy.

Although only one-third of cats have survived for a long time, the 20 cats in this study provide the basis for future studies with GC376 and other antiviral drugs that will follow. Not all cats will be treatable, but that shouldn't stop the effort. In this limited study, almost all treated cats returned to normal health, albeit for only a few weeks or months. It is important to be aware of the universality of viral pathogens and to take advantage of the pioneering development of drugs that are used clinically in the treatment of human diseases such as HIV / AIDS, hepatitis C, MERS, SARS, Ebola and influenza.

Conclusions

Inhibition of FIPV 3CLpro by GC376 was shown to be effective under the study conditions and led to a reduction in virus replication and remission of disease symptoms in cats with naturally occurring FIP outside the CNS. However, persistent remission in this study occurred earlier in kittens less than 18 weeks of age with acute wet FIP or in cats with dry FIP limited to mesenteric lymph node and is less likely to occur in cats older than 18 weeks with dry, mixed or the ocular form of FIP. Failure to achieve permanent remission was associated with either a high incidence of neurological disease during or after treatment or a recurrence of abdominal lesions. Antiviral therapy appeared to slow the progression of neurological disease but failed to reverse it at the dose used in this study. The cause of recurrence of extra-neurological disease during treatment has not been determined, but was not related to mutations in the protease-binding region.

Footnotes

Received: 3.8.2017

Additional material: Informed consent form of the owner.

Conflict of interests: YK, KOC and WCG have patent claims on protease inhibitors. Other authors do not represent any potential conflicts of interest in connection with the research, authorship or publication of this article.

Financing: The main support for this study was made possible by a grant from the Morris Animal Foundation, Denver, CO, USA. Additional funding for technical support and animal care was provided by Philip Raskin Fund, Kansas City, SOCK FIP, National Institutes of Health grant R01AI109039, and the Center for Pet Health, University of California, Davis, CA, USA.

References

1.Prokofiev, MM, Kochetkov, SN, Prassolov, VS. Therapy of HIV infection: current approaches and prospects. Acta Naturae 2016; 8: 23–32.
Google Scholar | Crossref | Medline
2.Carter, W., Connelly, S., Struble, K. Reinventing HCV treatment: past and future perspectives. J Clin Pharmacol 2017; 57: 287–296.
Google Scholar | Crossref | Medline
3.Kim, Y, Lovell, S, Tiew, KC. Broad-spectrum antivirals against 3C or 3C-like proteases of picornaviruses, noroviruses, and coronaviruses. J Virol 2012; 86: 11754–11762.
Google Scholar | Crossref | Medline
4.Kim, Y, Mandadapu, SR, Groutas, WC. Potent inhibition of feline coronaviruses with peptidyl compounds targeting coronavirus 3C-like protease. Antiviral Res 2013; 97: 161–168.
Google Scholar | Crossref | Medline
5.Kim, Y, Shivanna, V, Narayanan, S. Broad-spectrum inhibitors against 3C-like proteases of feline coronaviruses and feline caliciviruses. J Virol 2015; 89: 4942–4950.
Google Scholar | Crossref | Medline
6.Kim, Y, Liu, H, Galasiti Kankanamalage, AC. Reversal of the progression of fatal coronavirus infection in cats by a broad-spectrum coronavirus protease inhibitor. PLoS Pathog 2016; 12: e1005531.
Google Scholar | Crossref | Medline | ISI
7.Miller, FG, Brody, H. What makes placebo-controlled trials unethical? Am J Bioethics 2002; 2: 3–9.
Google Scholar | Crossref | Medline
8.Chiodo, GT, Tolle, SW, Bevan, L. Placebo-controlled trials good science or medical neglect? West J Med 2000; 172: 271–273.
Google Scholar | Crossref | Medline
9.Van Kruiningen, HJ, Ryan, MJ, Shindel, NM. The classification of feline colitis. J Comp Pathol 1983: 93: 275–294.
Google Scholar | Crossref | Medline | ISI
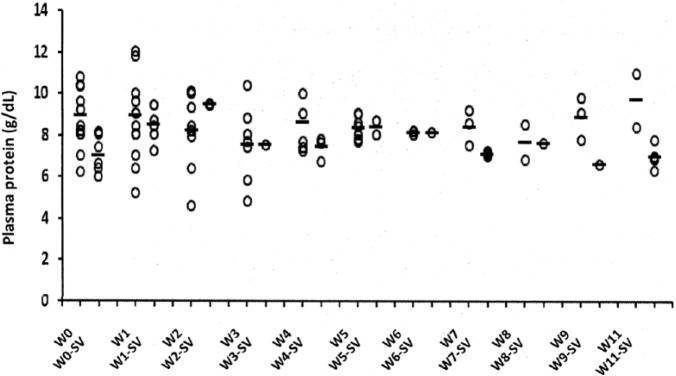
10.Pedersen, NC, Eckstrand, C, Liu, H. Levels of feline infectious peritonitis virus in blood, effusions, and various tissues and the role of lymphopenia in disease outcome following experimental infection. Vet Microbiol 2015; 175: 157–166.
Google Scholar | Crossref | Medline | ISI
11.Pellerin, M, Lopez-Aquirre, Y, Penin, F. Hepatitis C virus quasispecies variability modulates nonstructural protein 5A transcriptional activation, pointing to cellular compartmentalization of virus-host interactions. J Virol 2004; 78: 4617–4627.
Google Scholar | Crossref | Medline
12.Pedersen, NC, Allen, CE, Lyons, LA. Pathogenesis of feline enteric coronavirus infection. J Feline Med Surg 2008; 10: 529–541.
Google Scholar | SAGE Journals | ISI
13.Pedersen, NC. A review of feline infectious peritonitis virus infection: 1963–2008. J Feline Med Surg 2009; 11: 225–258.
Google Scholar
14.Pedersen, NC. An update on feline infectious peritonitis: virology and immunopathogenesis. Vet J 2014; 201: 123–132.
Google Scholar | Crossref | Medline
15.Pedersen, NC, Liu, H, Durden, M. Natural resistance to experimental feline infectious peritonitis virus infection is decreased rather than increased by positive genetic selection. Vet Immunol Immunopathol 2016; 171: 17–20.
Google Scholar | Crossref | Medline | ISI
16.Pedersen, NC, Liu, H, Gandolfi, B. The influence of age and genetics on natural resistance to experimentally induced feline infectious peritonitis. Vet Immunol Immunopathol 2014; 162: 33–40.
Google Scholar | Crossref | Medline
17.Clifford, DB. HIV-associated neurocognitive disease continues in the antiretroviral era. Top HIV Med 2008; 16: 94–98.
Google Scholar | Medline
18.Foley, JE, Lapointe, JM, Koblik, P. Diagnostic features of clinical neurologic feline infectious peritonitis. J Vet Intern Med 1998; 12: 415–423.
Google Scholar | Crossref | Medline | ISI
19.Mesquita, LP, Hora, AS, de Siqueira, A. Glial response in the central nervous system of cats with feline infectious peritonitis. J Feline Med Surg 2016; 18: 1023–1030.
Google Scholar | SAGE Journals | ISI
20.Pedersen, NC. Feline infectious peritonitis: something old, something new. Feline Pract 1976; 6: 42–51.
Google Scholar
21.Valcour, V, Sithinamsuwan, P, Letendre, S. Pathogenesis of HIV in the central nervous system. Curr HIV / AIDS Rep 2011; 8: 54–61.
Google Scholar | Crossref | Medline
22.Joseph, SB, Arrildt, KT, Sturdevant, CB. HIV-1 target cells in the CNS. J Neurovirol 2015; 21: 276–289.
Google Scholar | Crossref | Medline
23.Spudich, S, Gonzalez-Scarano, F. HIV-1-related central nervous system disase: current issues in pathogenesis, diagnosis and treatment. Cold Spring Harb Perspect Med 2012; 2: a007120
Google Scholar | Crossref | Medline
24.Cavalcante, LN, Lyra, AC. Predictive factors associated with hepatitis C antiviral therapy response. World J Hepatology 2015; 7: 1617–1631.
Google Scholar | Crossref | Medline
25.Saunders, BM, Cooper, AM. Restraining mycobacteria: role of granulomas in mycobacterial infections. Immunol Cell Biol 2000; 78: 334–334.
Google Scholar | Crossref | Medline
26.Smyk-Pearson, S, Tester, IA, Klarquist, J. Spontaneous recovery in acute human hepatitis C virus infection: functional T-cell thresholds and relative importance of CD4 help. J Virol 2008; 82: 1827–1837.
Google Scholar | Crossref | Medline
27.Legendre, AM, Bartges, JW. Effect of polyprenyl immunostimulant on the survival times of three cats with the dry form of feline infectious peritonitis. J Feline Med Surg 2009; 11: 624–626.
Google Scholar | SAGE Journals | ISI
28.Legendre, AM, Kuritz, T, Galyon, G. Polyprenyl immunostimulant treatment of cats with presumptive non-effusive feline infectious peritonitis in a field study. Front Vet Sci 2017; 4: 7.
Google Scholar | Crossref | Medline

Brief Personal Biography - Niels C. Pedersen

The original biography, which was written by Niels Pedersen himself on January 31, 2021 at my request in our e-mail communication.
English version: Brief Personal Biography - Niels C. Pedersen

Niels C. Pedersen

Before college, I never thought about being a vet, even though I grew up on a poultry farm in Southern California and had all kinds of animals. In 1957, as a high school student, I moved to southern Nevada and worked as a volunteer on a local ranch with cattle that roamed large areas of state land. After joining the University of Nevada in Rene, my goal was to be a teacher of professional agriculture. In my second year, I was inspired by a course I took in the field of Veterinary Sciences, which was taught by veterinary researcher Dr. Donald Marble. He opened my eyes to a career in veterinary medicine, which I hadn't even thought about before his course. I completely fell for it and enrolled in a veterinary school at the University of California, Davis in 1963. I loved the veterinary school and considered studying veterinary medicine the greatest educational experience in biology and medicine available. My first experience with feline infectious peritonitis (FIP) came in 1964, when I was working with a doctoral student on a veterinary pathology program. The cause of FIP was not known at the time and there was no animal or human disease that resembled it. My first professional article, which I co-authored and was published in 1967, drew on this work. It was at the veterinary school that my interest in cat medicine grew, mainly because of my love for them and my experience with wild cats on my father's poultry farm. . In teaching, but also in clinical practice, I realized a great lack of knowledge about cats and their diseases. As an older student, I was most interested in infectious and immunological diseases with an emphasis on cats and dogs. This was a great opportunity for someone who originally wanted to be a cattle doctor. In 1967-68, I completed an internship in the field of medicine and surgery of small animals at Colorado State University and then traveled with my wife and young daughter to Australia, where I completed my doctoral studies at the National University of Australia, John Curtin School of Medical Research in the field of experimental pathology and immunology. My three years in Canberra have been the second greatest educational experience of my life and have led me to a lifelong fascination with the Australian outback, especially the flora of Western Australia. I received my PhD from ANU in late 1971 and returned to UC Davis Faculty of Veterinary Medicine in early 1972 to research cancer. This did not suit me very well, but fortunately my dean recognized my clinical abilities and asked me to join the clinical faculty as an assistant professor. I've stayed in Davis ever since. I retired in 2010 as Professor Emeritus. I remained active in research at school until 2020, when I retired definitively.

The years I spent at UC Davis as a faculty member are full of memories and experiences. I have been an active small animal internal medicine clinician for 17 years, teaching infectious diseases, immunological diseases and cat medicine for 21 years, and then spending most of my time on administration and research. I served as chair of the department and later was director of the Veterinary Genetic Laboratory and founder and director of the Center for Pet Health. My main research interests have been feline infectious diseases, which has enabled me to make a significant contribution to our understanding of feline leukemia (FeLV), calicivirosis, herpesvirus and feline immunodeficiency virus (FIV). However, I was most obsessed with feline coronavirus and its association with feline infectious peritonitis. I have found that feline coronavirus is related to canine and pig coronavirus, and that it exists as a ubiquitous and mostly non-pathogenic feline enteric virus (so-called feline enteric coronavirus - FECV). The most important finding was the relationship of FIP to FECV and the postulate that FIP is a specific mutation of FECV that is similar but unique to each cat. Gaining this knowledge was not easy, because the FIP revealed its secrets only bit by bit and with great reluctance gradually over several decades. We now have almost complete knowledge of how the FIP virus is formed and how it causes the various clinical forms of FIP. Although we understand how FIP viruses cause disease, all attempts to develop protective vaccines have failed. This has led to studies of how host and environmental factors affect the occurrence of FIP. Although we already understood this factor relatively well, and based on this knowledge, we were able to reduce the incidence of FIP, FIP continued to be the main killer of cats. Sometime around 2015, I realized that we would probably not be able to effectively prevent FIP, and that we should try to find a cure instead. The treatment option was based on the growing use of antiviral therapy for human diseases caused by herpesvirus, influenza virus, HIV and hepatitis C virus. Experience in the treatment of hepatitis C, which is also caused by RNA virus, was particularly important. Viral protease inhibitors have been particularly noteworthy in the treatment of infectious hepatitis C. My attention was drawn to an article on animal RNA virus protease inhibitors from researchers at Kansas State University. This led to the first important collaboration and discovery that a viral protease inhibitor called GC376 can cure FIP in about one-third of cats or more. Subsequent research into another class of antiviral drugs, called nucleoside analogues, for the Ebola virus has led to collaboration with scientists from Gilead Sciences on one of their compounds, GS-441524. Over the course of two years, two completely different antiviral drugs have been discovered that are able to cure FIP. The rest is history - In the last two years, thousands of cats have been cured from the FIP using GS-441524 worldwide.

In the life and career of a scientist, it is not often that he can be involved in almost every stage of learning about a new infectious disease such as FIP, and end his career by finding a cure. The first mention of the FIP dates back to the late 1950s, and there is no evidence that it existed much earlier. Therefore, in a sense, FIP in cats is similar to COVID-19 in humans, and the fact that both diseases are caused by coronavirus should not go unnoticed. Hopefully, researchers studying COVID-19 will not take 50 years to understand and find a cure for SARS-CoV-2 infection. I am satisfied with my career and my contribution to the health of cats on many fronts, not only the FIP. But the FIP has always been a worthy adversary that has caught my attention. There is still much to be learned, and I hope that the next generation will continue to study this fascinating disease.

-Niels C. Pedersen, January 31, 2021

FIP and Polyprenyl Immunostimulant (PI)

Original article: FIP and Polyprenyl immunostimulant (PI) published on the UC Davis website.

Based on the results presented so far, CCAH cannot recommend PI as a means of prolonging the life of cats in any form of FIP.

Polyprenyl Immunostimulant

Polyprenyl immunostimulant (PI) is classified as a biopharmaceutical by the USDA and is manufactured by Sass and Sass in Tennessee. PI received a conditional license from the USDA as a therapeutic to treat the "symptoms" of feline herpesvirus infection. According to the Sass and Sass websites, they are conducting research into its use in the treatment of FIP and other pet diseases. Although not approved by the USDA for the treatment of FIP, it is currently commonly used to prolong the lives of cats with milder forms of FIP. It has not shown any benefit in the treatment or prolongation of the life of cats with wet FIP or cats with signs of serious illness at the beginning of treatment. Although, according to the web and according to some individuals, it provides an opportunity to prolong the life of cats with FIP, especially milder dry forms, it is important to examine what is known about the effectiveness of PI when used for this purpose. For a cat of average size and with a standard dosage, PI can cost more than $ 400 a month, and these costs can add to the associated veterinary expenses.

The first report on the use of PIs for the treatment of FIP was an article Effect of Polyprenyl Immunostimulant on the survival times of three cats with the dry form of feline infectious peritonitispublished by Dr. Al Legendre and colleagues in 2009. This study included three cats with dry FIP treated with polyprenyl immunostimulant. Two of the three cats were still on treatment and alive and well 2 years after diagnosis. The third cat survived 14 months, but was treated for only 4.5 months. However, it is important to know that these three cats suffered from a disease limited to the intestinal lymph nodes and that two of the cats showed no signs of disease at the time of diagnosis (one was detected during castration and the other on routine palpation for blood donation). The third cat was a bit neglected and had a palpable intestinal lymph node. Blood tests and lymph node biopsies were compatible with the diagnosis of FIP. All three cats were treated with PI. One cat treated for 27 months remained clinically normal, although it still had blood changes indicating subclinical disease. The second cat was treated for 10 months and looked normal with lymph node enlargement. The third cat was treated for the first 3 months, continued to lose weight, and treatment was discontinued. This cat died 11 months later at the FIP. The authors believed that these results demonstrated some therapeutic benefit of PI treatment, assuming that all cats with FIP usually die within 200 days or less. The importance of treatment in these three cats is questionable. Not only were their numbers small, but some cats with no or minimal signs of disease and lesions located in the abdominal lymph node recover spontaneously over time. In addition, only one in three cats seems to have recovered completely; one died of FIP and one had symptoms of subclinical infection at the end of treatment. The authors concluded that "further studies are needed to assess the potential of the polyprenyl immunostimulant" and only cats with a well-documented dry form of FIP will be considered for inclusion in the next study.

A follow-up study of 102 cats diagnosed with dry FIP Dr. He presented the legend in 2012 at the ACVIM forum. The results of this study were as follows: “The data of the cats suspected of being FIP were thoroughly verified and cats that met the inclusion criteria were admitted to the study. Based on previous experience, we did not see any benefit of PI in cats with the wet form of FIP and these were excluded from the study. A total of 58 cats with a diagnosis of "dry" form of FIP treated with polyprenyl immunostimulant were included in the study. We started with a total of 102 cats, but cats that died before starting PI treatment, cats that died before the week of PI treatment, and cats that did not have a follow-up assessment were excluded. The study included a wide variety of purebred and domestic shorthair cats. Cats had an ocular, neurological, and abdominal form of dry FIP, with the abdominal form being the most common. 9% cats had unclear symptoms without affecting a specific organ. Three cats lived longer than 365 days (5%), 22% cats were alive for at least 165 days. PI appears to improve the well-being of treated cats. "

Notably, 44 of the total cats included in the study were excluded because they either died before treatment, died less than one week after administration, or were not re-available / examined for follow-up evaluation. Two of the groups excluded from the study had apparently severe disease and it is highly likely that most cats unavailable for follow-up either died or did not respond to treatment and also had severe disease. Of the 58 cats with milder dry FIP that remained in the study, 9% (5/58) had indeterminate symptoms without specific organ involvement, ie the disease was not confirmed. Also including these cats, only 22% (12/58) was alive after 165 days and only 5% (3/58) of these cats was alive after 365 days.

Owners who are considering using PI therapy in their cat with FIP should carefully consider these previous findings as well as the cost of treatment. Cats with wet FIP or severe dry FIP do not respond to this treatment. Of the cats with a lighter form of dry FIP, only 5% will still be alive a year later. The only claim made by the researchers or the manufacturer is that PI treatment may prolong life in a subset of cats with milder dry FIP. Because this study did not include any placebo controls, and given the fact that a small percentage of cats with dry FIP can live without PI treatment for many months and even years, this claim should be taken with some skepticism. Based on the results presented so far, CCAH cannot recommend PI as a means of treating or even prolonging the life of cats with any form of FIP.

Phosprenyl

Polyprenyl immunostimulant as a potential treatment for cats with FIP has an interesting history that extends from Russia to the United States. The research and chemical structure of PI is based on a biological "plant extract" called Phosprenyl, which is used in Russia to treat a wide range of viral infections in many species of animals. PI may thus be of Russian origin.

Translator's note: Considering the price of PI and its highly questionable effect and the necessity of endless "treatment", it is questionable whether it makes sense to invest money in this apparently only supportive therapy, or rather go for real treatment with GS441524, at the end of which there is a truly healthy cat. For me, the choice is clear.

Sources:

History of feline infectious peritonitis studies

Original article: UC Davis has a long history of studying feline infectious peritonitis

Smokey

Research into feline infectious peritonitis (FIP) at UC Davis began in 1964 with Dr. Niels Pedersen, who was a veterinary student at the time, and Dr. Billy Ward, a graduate of veterinary pathology at the time. Pedersen later became Professor of Medicine and Epidemiology and Founding Director of CCAH.

Ward and Pedersen published their research on the FIP in 1969. Pedersen was also interested in the disease during his internship at Colorado State University and his doctoral studies at the National University of Australia. He continued his research on FIP and other feline infectious diseases after returning to UC Davis and the Veterinary School in 1972. The FIP research program is still active at UC.

Pedersen is a world-renowned authority in the field of FIP and has 45 important scientific articles and a number of chapters and reviews in the veterinary literature. His textbook "Cat breeding, diseases and management in a multi-cat environment" is still considered a classic among breeders. Pedersen retired in 2013, but continues to pursue an active FIP research program as Professor Emeritus. Current research continues to focus on how FIPV causes the disease itself, the genetic and environmental factors that affect the incidence of the disease, and most recently on the use of specific drugs to target FIPV replication in cats.

Pedersen is fortunate to have had the support of private organizations such as the Winn Feline Foundation, the Morris Animal Foundation, Save Our Cats and Kittens (SOCK) and SOCK FIP, private foundations and purebred cat registries, and many individual donors. “As my career draws to a close, I am delighted to be joined by my colleagues, including Dr. Brian Murphy and Dr. Patty Pesavento, who continue to uphold the School of Veterinary Medicine’s reputation as one of the leading research groups on feline coronavirus infections such as FECV and FIPV,” says Pedersen. “We all agree that FIP is one of the most complex infectious diseases of humans and animals.” Fortunately, Pedersen’s more than half a century of research has helped unravel much of this complex puzzle.

Many key discoveries about FIP come from our school and Pedersen's laboratory, including the first coronary virus spread in tissue culture, recognition of its relationship to common coronaviruses of other species, development of an antibody test for feline coronavirus, and the discovery that FIP virus (FIPV) is an unusual mutation. and mostly non-pathogenic feline enteric coronavirus (FECV). Attempts to develop vaccines against the disease have failed, leading to a study of how to reduce the incidence of the disease in kennels, shelters and other high-risk environments through preventive measures in cat breeding. Dr. Pedersen has also completed several studies on the role of hereditary factors in predisposing to FIP. Genetic susceptibility and resistance have been found to be very complex, and attempts to increase resistance by selectively breeding naturally immune females and males have led to increased rather than decreased susceptibility. Kinship crosses have been identified as a major hereditary risk factor.

FIP survivors
Moon
Bubba

Bioavailability GS-441524

The original article collected from various pieces of information.

In this short post, I would like to focus on the bioavailability of GS441524 when taken orally.

Many of you are probably wondering why GS441524 exists primarily as a solution for injection, or why tablets are so expensive. The fundamental problem is that GS441524 (but also Remdesvir) falls into BCS class IV (low permeability, low solubility), which indicates a substance with poor bioavailability. BCS stands for Biopharmaceutics Classification System, which is a system used to classify drugs according to their solubility and permeability. Bioavailability means the proportion of an administered dose of unchanged substance that enters the systemic circulation. This is one of the main pharmacokinetic properties of drugs. By definition, the bioavailability of a drug administered intravenously is 100%. Bioavailability is lower with any other route of administration. That is why pharmacokinetics play one of the main roles in a clinical study of a new drug, which, among other things, aims to determine the dosage for a given form of drug administration (eg intravenous - subcutaneous - oral). When orally administered pure GS441524, the bioavailability appears to be only about 10%. For this reason, the possible administration of the solution for injection by oral route would probably not bring the desired effect (but maybe someone will try it, I'm just not sure if the life of their own cat is building on it). GS441524 shows very poor penetration into the gastrointestinal tract and a very strong first-pass effect. The first-pass effect is a phenomenon in drug metabolism, where the drug concentration is significantly reduced before the drug enters the systemic circulation (and we are in bioavailability). It is a part of the substance that is metabolised during the absorption process, which is associated with the liver (liver) and the intestinal wall.

And how is this problem solved in tablets? In order for the oral form of any drug to be created at all (and this is also the primary goal of all drug manufacturers), it is necessary to ensure, resp. increase its bioavailability. To a limited extent, this can be achieved with certain additives, but in some cases it is not possible at all. Therefore, some drugs exist only in injectable form, while others have both tablet and injectable form. One of the substances that can increase the bioavailability of the drug is microcrystalline cellulose. In the case of GS441524, it can theoretically increase its bioavailability from 10 to 50%. Ultimately, however, this means that in order to achieve a similar therapeutic effect as when injecting (ie a similar concentration of the active substance in the blood plasma), it is necessary to double the absolute amount of the active substance in the tablet. This is one of the reasons why the content of GS441524 in tablets is stated as the equivalent of GS441524, but it does not reflect its actual amount, which can be, for example, double (I do not know the exact numbers).

Another way to solve the problem is to modify the active substance molecule in such a way as to increase its bioavailability and that its metabolism after oral administration results in the active substance itself.

Given that the manufacturers of oral forms of GS441524 keep secret the specific manufacturing process and the exact composition of the tablets, I have no information about how they achieved the result. For example, Mutian states that in Mutian Xraphconn capsules for the treatment of FIP, it uses an active ingredient that it claims is not GS441524 (which also allows it to circumvent patent rights). By the way, it lists INONOTUS OBLIQUUS FRUITING BODY (a woody mushroom also known as Chaga) as the active ingredient, which is obvious nonsense, because I don't know that this mushroom treats FIP. 🙂

Either way, making a tablet that actually works is clearly not a trivial matter. And this may be one of the reasons why tablets are significantly more expensive than injectable solutions.

Sources:

Treatment of FIP in cats with Remdesivir

Original article: Treatment of FIP in cats with Remdesivir
Richard Malik DVSc PhD FACVSc FASM

Until recently, the diagnosis of FIP for a feline patient was a death sentence. Although omega-interferon and polyprenyl immunostimulant had some effects in some cases, most cats and kittens diagnosed with FIP died or euthanasia was required due to poor condition.

Figure 1. (A) BOVA Remdesivir reconstituted and ready for treatment. (B) The pathway that Remdesivir takes intracellularly to activate as GS-441524

That all changed a few years ago when the lifelong research of FIP Professor Niels C. Pedersen of UC Davis culminated. Niels first managed to save the lives of several cats with FIP with the protease inhibitor GC-376, and soon after showed that the nucleoside analog GS-441524 is even more effective in treating FIP, although the required dose depended on whether there was ocular or CNS involvement. . GS-441524 was a drug developed by the American company Gilead, which unfortunately did not show interest in further research into the molecule for veterinary use in the treatment of FIP. To fill the gap for effective FIP therapy, various companies have begun to manufacture GS-441524 and sell it on the black market. Although it was very expensive, the availability of quality GS-441524 provided determined cat owners with a way to save cats with wet or dry FIP, although obtaining this drug was complicated, usually associated with the help of a Facebook group. Unfortunately for cat lovers, APVMA and the Australian Veterinary Practitioner Board eventually made the import of GS-441524 and its use for veterinary purposes significantly more difficult, with repressive measures for veterinarians who wanted to help cats with FIP.

It is ironic that the COVID 19 pandemic has solved this problem. Gilead has developed remdesivir (GS-5734) for the treatment of human coronavirus disease. The drug received a temporary TGA marketing authorization in June 2020 for the treatment of SARS-Cov-2 infections in human patients. This process would normally take several years, but COVID accelerated it. Remdesivir is essentially GS-441524 with the addition of several additional phosphate groups to improve intracellular penetration (Figure 1B). Because remdesivir is an approved human drug, it can also be used off-label in veterinary practice, such as the treatment of FIP in cats. This circumvented problems with the use of an unlicensed medicine purchased on the black market and related problems with unproven efficacy, purity and consistency.

Figure 2. Dry FIP with pyogranulomatous inflammation of the intra-abdominal lymph nodes. Instead of exploratory laparotomy, lymph node biopsy, histology and immunohistology, it could be more cost-effective to try a 3-day intravenous Remdesivir treatment.

BOVA Aus was able to provide a reliable source of remdesivir. Studies in Australia have determined shelf life and confirmed in vitro efficacy against coronaviruses. We have been using it in clinical practice for the treatment of FIP for the last 6 weeks. Some of these cases were newly diagnosed cats, while others were cats that had already improved with GS-441524 obtained from the black market, which subsequently became unavailable. Several cases of wet and dry FIP have been treated. Even with the small number of cats, remdesivir appears to be very effective in treating FIP infections. Its subcutaneous administration is slightly easier compared to GS-441524, and it appears to be slightly less painful. It is supplied in a 100 mg vial, which is diluted with 9 ml of sterile water for injections to give a solution with a concentration of 10 mg / ml (10 ml vial after dilution).

In newly diagnosed cats with severe disease, we opted for the intravenous administration of remdesivir at a high starting dose (10 mg / kg dissolved in 10 ml saline and administered over 10 minutes) during the first 3 days of treatment, thus achieving a rapid onset of antiviral activity; The clinical signs of cats improved significantly during the initial therapy within 2-3 days. Cats then switch to subcutaneous treatment, usually at a lower dose. For common cases of FIP, we used 5-6 mg / kg once daily (SIUD) because remdesivir is thought to be approximately as effective as GS-441524 (Niels Pedersen, personal communication). In case of overt eye disease, a dose of 8 mg / kg SID is recommended and cats with neurological FIP with CNS symptoms are given 10 mg / kg SID. Treatment is then continued by daily subcutaneous injections for another 2-3 months. In cats for which SC injections were painful, we used gabapentin and / or buprenorphine for sedation / analgesia, and in some cases we introduced a new cephalic catheter every 5 days, which allowed the owners intravenous administration. In situations where owners could not afford the entire treatment, or when the injections were too painful, we used mefloquine (62.5 mg 2-3 times a week; obtained from BOVA or a local pharmacy) for initial work-based antiviral treatment after initial treatment with Remdesivir. Jacqui Norrisa and colleagues from the University of Sydney.

Figure 3. Which cat has FIP and is being treated with remdesivir?

The main advantage of FIP Remdesivir treatment is that the active substance we use is present in an approved medicine for human use. It is just a matter of writing a prescription with the name and address of the client, the name of the patient and the dose to be administered. BOVA can usually prepare and deliver vials to any veterinarian in Australia within 24-48 hours. At present, the cost per 100mg vial is $ 250 plus GST and postage, although it is possible that the price will decrease over time due to larger orders. We believe that most owners will feel much better if they get the product from a well-known Australian company than to send money abroad and hope that black market drugs will get safely from China to Australia.

Veterinarians who want to know more about this treatment option or have general questions about FIP can contact me by email (richard.malik@sydney.edu.au). The diagnosis of FIP is beyond the scope of this newsletter, but effusive cats are most easily diagnosed by cytology and effusion analysis, followed by immunohistochemistry at VPDS, University of Sydney (easily arranged via Vetnostics, QML, ASAP, VetPath, Gribbles or IDEXX). Dry FIP is more problematic because it usually requires an accurate aspiration biopsy of pyogranulomatous lesions in the liver, kidneys, or abdominal lymph nodes. We found that 3 days of intravenous Remdesivir therapy could be used as a cost-effective therapeutic test in cats with dry FIP as an alternative to biopsy of intra-abdominal structures in exploratory laparotomy, as FIP cases rapidly improve most clinical symptoms. If veterinarians do not want to start treatment with Remdesivir themselves, we can recommend veterinarians interested in FIP treatment who would like to accept such cases.

Resources

Kim, Y .; Liu, H .; Galasiti Kankanamalage, AC; Weerasekara, S .; Hua, DH; Groutas, WC; Chang, KO; Pedersen, NC Reversal of the progression of fatal coronavirus infection in cats by a broad-spectrum coronavirus protease inhibitor. PLoS Pathog. 2016, 12, e1005531.

Pedersen, NC; Kim, Y .; Liu, H .; Galasiti Kankanamalage, AC; Eckstrand, C .; Groutas, WC; Bannasch, M .; Meadows, JM; Chang, KO Efficacy of a 3C-like protease inhibitor in treating various forms of acquired feline infectious peritonitis. J. Feline Med. Surg. 2018, 20, 378–392.

Murphy, BG; Perron, M .; Murakami, E .; Bauer, K .; Park, Y .; Eckstrand, C .; Liepnieks, M .; Pedersen, NC The nucleoside analog GS-441524 strongly inhibits feline infectious peritonitis (FIP) virus in tissue culture and experimental cat infection studies. Vet. Microbiol. 2018, 219, 226–233.

Pedersen, NC; Perron, M .; Bannasch, M .; Montgomery, E .; Murakami, E .; Liepnieks, M .; Liu, H. Efficacy, and safety of the nucleoside analog GS-441524 for treatment of cats with naturally occurring feline infectious peritonitis. J. Feline Med. Surg. 2019, 21, 271–281

Dickinson PJ, Bannasch M, Thomasy SM, et al. Antiviral treatment using the adenosine nucleoside analogue GS-441524 in cats with clinically diagnosed neurological feline infectious peritonitis. Journal of Veterinary Internal Medicine. 2020. doi: 10.1111 / jvim.15780.

McDonagh, P .; Sheehy, PA; Norris, JM Identification and characterization of small molecule inhibitors of feline coronavirus replication. Vet. Microbiol. 2014, 174, 438–447.

Coronavirus in pets and humans: know the differences!

Original article: Coronavirus in pets and humans: learn the differences! (6.4.2020)
Translation: 17.1.2021

There is currently no evidence to suggest that humans infected with humans play a role in the spread of COVID-19. (*)

COVID-19 is a disease caused by a new type of coronavirus SARS-CoV-2. As the number of new cases grows worldwide, there is a growing concern for human and animal welfare, and important questions arise regarding prevention and best practices in the event of a positive diagnosis. In addition, another major doubt has arisen among pet owners: can dogs and cats also become infected, or can they transmit the virus?

So far, there are only a few known cases of pet infections around the world, including two dogs in Hong Kong and two cats in Belgium. Both dogs showed no signs of disease, but one cat had respiratory and digestive disorders. In addition, he had US Department of Agriculture The Malaysian Tiger also tested positive at the Bronx Zoo in New York.

According to the data World Organization for Animal Health (OIE) a World Health Organization (WHO), there is as yet no evidence to suggest that humans infected with humans play any role in the spread of COVID-19.

Coronaviruses are a large group of viruses that are quite common in animals. There are four genera of the family Coronaviridae (Alphacoronavirus, Betacoronavirsus, Gammacoronavirus and Deltacoronavirus), which cause different diseases in different species of animals. The WHO emphasizes that people are occasionally infected with these viruses, which can spread to other people. For example SARS-CoV has been associated with civets and MERS-CoV is transmitted by single-humped camels.

Relationship with animals

Possible animal sources of COVID-19 have not yet been confirmed. Although the OIE claims that current evidence suggests that the COVID-19 virus came from an animal source, investigations are underway to find that source (including relevant species) and to determine the possible role of the animal reservoir in the disease.

To understand these differences, we spoke to our veterinarians. Hervé Poulet, the global leader in vaccines for pets and horses, shares the view that, despite the current lack of evidence that pets can transmit COVID-19, the OIE emphasizes that people who have the disease should avoid being very close. contact with your pets. Furthermore, they should follow good hygienic practices when handling and caring for them - this is a behavior that we should always follow.

"Cats and dogs can also be affected by their specific coronavirus, for example canine enteric coronavirus (CCoV), which belongs to the genus Alphacoronavirus and causes mild enteritis in dogs and infects cells in the gut, ”says Hervé.

Jean-Philippe Tronel, global technical director for pet vaccines, notes that vaccination against this animal disease already exists and is present in polyvalent vaccines for dogs in North America and some countries in Asia and Latin America. In addition, in the context of felines, there is a feline coronavirus (FCoV) that can cause a serious feline disease known as feline infectious peritonitis. The vaccine against it is available in some countries in Europe, Asia and North America.

It's not the same coronavirus

In contrast, people may be positive for presence beta-coronaviruses - such as SARS-CoV-2, responsible for the current pandemic; SARS-CoV, which originally caused Severe Acute Respiratory Syndrome in China in 2002 (SARS); a MERS-CoV, responsible for Middle East Respiratory Syndrome (MERS), which appeared in 2012 in Saudi Arabia. It is important to emphasize that there is no evidence of human-to-animal transmission in both diseases.

"Given these differences, the treatment options for different types of coronavirus are certainly not the same. Among the growing panic over the COVID-19 pandemic, there have been reports that people are seeking vaccines against canine and feline coronavirus as a desperate - and wrong - way to immunize. For this reason, it is important to emphasize that these vaccines are exclusively for dogs or cats. There are no clinical trials to ensure safety and efficacy in humans, ”says Hervé.

Last but not least, Karin Botteon, a veterinary consultant in the pet segment in Brazil, emphasizes that in case of any doubts, more than ever, it is crucial to always seek the advice of a veterinarian during this pandemic period. It is essential to strengthen the need for preventive medicine for pets, including proper adherence to vaccination programs.

"Because most countries in the world are currently facing a series of restraints, it is very important that pet owners contact their veterinarians to obtain correct and professional information on best practices and boards of directors for their own country or even region. Remember: when animals are healthy, people are also healthier, "concludes Karin.

(*) The situation regarding COVID-19 is constantly evolving. Research into all aspects is taking place around the world, including the mode of infection, and there is no way to go as far as possible to obtain as much information as possible. From what we know so far, there is no scientific knowledge about any transmission of the disease from pets to humans.

We follow all related research results and recommendations of international experts, especially the World Organization for Animal Health (OIE) and the World Health Organization (WHO). We will share these updates when they become available.

Translator's Note: There is only 63% similarity between SARS-CoV-2 and FCoV, and even so, it is limited to only about 1/4 of the genome.

Pharmacokinetic profile of oral mefloquine in clinically normal cats: Preliminary in vivo study of the potential treatment of feline infectious peritonitis (FIP).

Jane Yu, Benjamin Kimble, Jacqueline M. Norris and Merran Govendir
Sydney School of Veterinary Science, Faculty of Science, The University of Sydney, Sydney, NSW 2006, Australia; jane.yu@sydney.edu.au (JY); benjamin.kimble@sydney.edu.au (BK); jacqui.norris@sydney.edu.au (JN); merran.govendir@sydney.edu.au
Original article: Pharmacokinetic Profile of Oral Administration of Mefloquine to Clinically Normal Cats: A Preliminary In ‐ Vivo Study of a Potential Treatment for Feline Infectious Peritonitis (FIP)
8.6.2020

Brief summary:

In the search for antiviral agents against feline coronaviruses and feline caliciviruses, mefloquine, a human antimalarial drug, has been shown to reduce the viral load of feline coronaviruses and feline calicivirus in infected cells. In this study, mefloquine was administered orally to seven clinically healthy cats twice a week in four doses, and blood mefloquine concentrations were measured to determine the pharmacokinetic profile - drug movement in the body. The maximum blood concentration of mefloquine was 2.71 ug / ml and was reached 15 hours after a single oral dose. Side effects of mefloquine in some cats included vomiting after feeding without food and a slight increase in symmetric dimethylarginine (SDMA), an early renal biomarker. This study provides valuable information on the profile of mefloquine in cats as an initial step to its research as a possible treatment for feline coronavirus and feline calicivirus infection in cats.

Abstract: The pharmacokinetic profile of mefloquine was investigated to preliminary study the potential treatment of feline coronavirus infections (such as feline infectious peritonitis) or feline calicivirus infections. Mefloquine was administered orally at a dose of 62.5 mg to seven clinically healthy cats twice a week in four doses, and plasma mefloquine concentrations over 336 hours were measured by high performance liquid chromatography (HPLC). The maximum plasma concentration (Cmax) after a single oral dose of mefloquine was 2.71 ug / ml and the time to Cmax (Tmax) was 15 h. The elimination half-life was 224 h. Plasma concentrations reached a higher level of 4.06 ug / ml when mefloquine was fed. Dosage side effects in some cats included vomiting after administration without food. A slight increase in symmetric dimethylarginine (SDMA) but not creatinine serum concentrations was observed. Mefloquine can provide a safe and effective treatment for coronavirus and calicivirus infections in cats. 

Keywords: mefloquine; feline infectious peritonitis; pharmacokinetics; coronavirus; calicivirus 

Introduction

Feline coronavirus (FCoV) is an alpha coronavirus that occurs in two distinct pathotypes that can be distinguished by biological behavior but not by morphology [1]. Although the two pathotypes belong to the same type of virus, different names are used - feline enteric coronavirus (FECV) and feline infectious peritonitis virus (FIPV). FECV is highly contagious by the fecal-oral route. The infection is usually asymptomatic or can cause mild diarrhea [1,2]. FIP is a deadly, immune-mediated disease caused by virulent FCoV biotypes known as feline infectious peritonitis virus (FIPV) in domestic and wild cats. When cats with FIP show clinical signs, life expectancy ranges from a few days to a few weeks for the effusive form and from a few weeks to a few months for the non-fusive form [3-6]. However, there are a small number of cats that can survive for several years [7,8]. Treatment options are traditionally limited, but recent experimental treatments using protease inhibitors and nucleoside analogs have yielded promising results [9-13], although these treatment options have not yet been registered for the treatment of cats. The lack of available treatment options exacerbates the need to explore other available antiviral treatments. In addition, the search for treatment targeting various aspects of FCoV replication is of therapeutic value, as combination therapy for other viral infections is associated with a higher rate of pathogen suppression and minimizing the development of antiviral resistance [14,15]. 

Feline calicivirus is an important and common cause of upper respiratory tract disease and oral ulceration in cats, with more virulent forms of the virus emerging recently, leading to an outbreak of systemic disease, which is often fatal and, like FIP, has no effective antiviral treatment. [16] 

In the search for antiviral agents against feline coronavirus and feline calicivirus, mefloquine, a human antimalarial, has been shown to inhibit FCoV viral load in infected Crandell feline kidney cells without cytotoxic effects [17]. Its inhibition of cytopathic effects and viral replication at low concentrations supports further investigation of this drug as a potential antiviral therapeutic. In our previous project, we developed an in vitro model to determine the extent and rate of hepatic clearance (Cl) of mefloquine [18]. In cats, mefloquine undergoes phase I hepatic metabolism but not phase II conjugative metabolism [18]. There is no evidence that mefloquine delays elimination in clinically healthy cats. Plasma protein binding of mefloquine is approximately 99 % in the plasma of clinically normal cats as well as in the plasma of cats with FIP [19].

As mefloquine is currently used for malaria prophylaxis, information on its availability is available, including absorption, distribution and rate and extent of elimination of the drug in adults and infants, with some information also available in dogs [20], but not at this stage. no information is available on the pharmacokinetic profile (PK) of mefloquine in cats other than plasma protein binding [19]. Therefore, in order to assess whether the administration of mefloquine as an antiviral has any therapeutic advantage, it is necessary to determine the pharmacokinetic profile of mefloquine in clinically normal cats in order to develop the dosage and frequency of doses. Recognition of the pharmacokinetic profile of mefloquine in a clinically normal cat is a transitional step that bridges preclinical observations of mefloquine to feline medication in the future. The aim of this study was to examine the pharmacokinetic profile of mefloquine when administered 62.5 mg (10-12 mg / kg) orally twice weekly. The second objective was to document any changes in hematological and / or biochemical analytes and physiological responses to mefloquine in this dosing regimen.

Materials and methods 

The animals 

Eight adult cats (4 females, 4 males) were acquired by Invetus Pty Ltd. (Casino, New South Wales, Australia), an animal research facility, from its clinically normal animals. Body weight ranged from 5.0 to 5.8 kg (average 5.4 kg). The cats were 3 to 7 years old (average 5.5 years). Cats were selected based on clinically normal physical examination, normal fitness score, and body weight ≥ 5 kg. Exclusion criteria included cats with an abnormal physical examination, underweight cats, or cats that took medication. Seven cats were originally selected for the study. The cats were housed individually in boxes at the kennel and supplied with food and water ad libitum. The selection of clinically normal cats, their dosing with mefloquine, blood collection and shelter was carried out by the company Invetus. This study was approved by the Wongaburra Research Center's Animal Ethics Committee as a USY F 18120 W project on August 29, 2019 and by the University of Sydney Animal Ethics Committee as Protocol 2019/1662.

Drug administration and sampling

The cats were given a mask for blood collection and anesthesia with isoflurane in 100 % oxygen, and 2-4 ml of blood was collected from the jugular veins using a 22 mm diameter needle. Blood was collected into lithium heparin tubes, ethylenediaminetetraacetic acid (EDTA) tubes and serum tubes for mefloquine quantification, hematology and biochemistry. A 250 mg tablet of mefloquine (Lariam, Roche, Millers Point, New South Wales, Australia) was quartered along the line on the tablet. For each cat, the dose was a quarter of a tablet or 62.5 mg of mefloquine. The weight of each quarter of the tablet was recorded for consistency of dosing. Mefloquine (62.5 mg) was administered orally to each cat on days 0, 4 (corresponding to 96 h), 7 (168 h) and 10 (240 h). The cats were then monitored for any adverse reactions 2 hours after dosing. To determine mefloquine plasma concentrations, serial blood samples were taken into lithium heparin tubes at time 0 (before treatment), 1, 2, 4, 8, 12, 24, 48, 96, 168, 240 and 336 h after drug administration. On mefloquine administration days other than the first administration day (t = 96, 168 and 240 h), blood samples were taken before the mefloquine dose, followed by wet or dry food for several minutes. Blood was also collected into EDTA and serum tubes for hematological and biochemical examination at 168 and 336 hours. The samples were centrifuged within 1 h after blood collection. Plasma and serum were immediately stored in a freezer (-20 ° C) within 90 minutes of blood collection. EDTA tubes were immediately shipped to Idexx East Brisbane, Qld. Australia, for hematological analysis. Serum tubes were sent to the Veterinary Pathology Diagnostic Services, The University of Sydney and the Idexx Reference Laboratory for biochemical analysis. Serum was also sent to the Idexx Reference Laboratory for analysis of serum symmetric dimethylarginine (SDMA) and creatinine. To determine plasma mefloquine concentrations, samples were analyzed at the Sydney School of Veterinary Science, The University of Sydney, within two months of blood collection. 

Drug analysis method and sample processing

The concentration of mefloquine in the samples was quantified by high pressure liquid chromatography (HPLC), and the plasma samples were adjusted according to a validated method [19]. 

Chemicals

Mefloquine, verapamil (as internal standard [IS]), sodium phosphate, trimethylamine and phosphoric acid were purchased from Sigma-Aldrich (Castle Hill, Sydney, New South Wales, Australia). Acetonitrile and HPLC grade methanol were purchased from Thermo Fisher Scientific (Macquarie Park, NSW, Australia).

HPLC conditions

The HPLC system consisted of a Shimadzu LC-20AT feed unit, a DGU-20A3 HT feed unit for solvent degassing, an SIL-20A automatic injector, a SPD-20A UV detector and a CTO-20A column furnace. Shimadzu LC Solution software (Kyoto, Japan) was used for chromatographic control, data collection and processing. Chromatographic separation was performed using a Polaris C18-A column (5 μm, 150 × 4.6 mm) with a 1.0 mm diameter Optic-guard C 18 precolumn (Choice Analytical, Thornleigh, NSW, Australia) while adjusting the column temperature. at 35 ° C. The isocratic mobile phase contained a mixture of 25 mM sodium phosphate with 0.5 L of TP 2 T triethylamine adjusted to pH 6.0 with phosphoric acid, acetonitrile and methanol (50:25:25) at a flow rate of 0.8 ml / min. For each sample, the injection volume was 10 μl and the total duration was 15 min. The diode array detector was set to a wavelength of 220 nm. 

Plasma mefloquine concentrations of 0.156, 0.313, 0.625, 1.25, 2.50 and 10.0 μg / ml were prepared by serial dilution for sample preparation. Solution IS was prepared in 100 % acetonitrile at a final concentration of 10 ug / ml. Feline plasma samples were used to prepare the standard curve. 

To extract proteins from plasma samples, 100 μl of acetonitrile containing 10 μg / ml IS was added to 100 μl of feline plasma samples. The samples were then vortexed and centrifuged at 14,000 g for 10 minutes. Ten microliters of supernatant was injected into the HPLC system for analysis. 

Pharmacokinetic analysis 

The data were evaluated by non-compartmental analysis, as the elimination phase was evident at only two time points, ie 48 and 96 h. The mean maximum plasma concentration (C max) and the time to C max (T max) of the first dose were determined by visual inspection of the plasma concentration-time curve of each cat over 96 hours. The difference in the natural logarithm of the plasma concentrations at 24 and 96 hours, ie the slope of the curve from 24 to 96 hours, gave. The elimination half-life was estimated using ln 2 / ke. Area under the curve (AUC0 ‐ t) at 96 h was calculated to the last measurable concentration using the linear trapezoidal method. Apparent volume of distribution was calculated as: 

V / F = (Dose / AUC) × (1 / ke), (1)

where F is the oral bioavailability that cannot be determined because intravascular (intravenous) administration of mefloquine to cats has not occurred. Apparent clearance was calculated as: 

Cl / F = V × ke. (2)

Area under the torque curve (AUMC00-96h ) was calculated as the sum of the AUC when each of the concentration data was multiplied by time. The average residence time was calculated as 1 / ke.   

Statistical analysis

Two cats were excluded from the statistical analysis due to vomiting. Mefloquine plasma concentration data for five cats (including cat E) at 24, 96, 168, 240 and 336 h were subjected to the Shapiro-Wilk normality test and all distributions were normal. However, SDMA concentrations were not normal at t = 0 h, but were normal at 168 and 336 h. Creatinine concentrations were normal at 0, 168 and 336 h. Mean plasma mefloquine concentrations were compared at 24, 96, 168, 240 and 336 h and were subjected to repeated on-way ANOVA measurements, as were mean SDMA and creatinine concentrations at 0, 168 and 336 h. Tukey's multiple comparison test was used to demonstrate whether the mean values at each time point differed significantly. Statistical analysis was accepted if p <0.05. Statistical analysis was performed using Graphpad Prism 8 (San Diego, CA, CA). 

The results

Following administration of 62.5 mg of mefloquine per cat, the mean dose was 11.8 mg / kg (median 12.3, range 10.8-12.5). The change in mefloquine plasma concentrations over 336 h (14 days) in seven cats is shown in Figure 1 and the actual mefloquine plasma concentrations of each cat at each time point are shown in Table 1. Figure 2 shows mefloquine plasma concentrations (ug / ml). during the first 24 hours. A single oral dose of mefloquine results in a Cmax of 2.71 μg / ml after the first dose, averaging 15 h (Tmax). Increases in mefloquine plasma concentrations were observed after 168, 240 and 336 h (Figure 1), after the second dose given just after 96 h, the third dose given just after 168 h and the fourth dose given just after 240 h, respectively when mefloquine was administered with food, with peak plasma concentrations reaching 4.06 μg / ml (average) after 240 h. One cat (cat C) vomited 15 minutes after dosing on day 0 (treatment 1). Mefloquine was re-administered to this cat on day 4 (treatment 2), but vomited approximately one hour after dosing and was therefore excluded from the study. Another cat (cat F) vomited 5 minutes after dosing on day 1 (treatment 1). This cat was successfully given a dose of mefloquine after feeding on the following day of treatment (96 h) and was re-enrolled in the study. This time, no vomiting was observed after dosing. Blood samples were taken from cat F at 168, 240 and 336 h as shown in Table 1. 

Figure 1. Mefloquine plasma concentrations (ug / ml) in seven cats over 336 hours (14 days after the first dose). Cats were treated with a dose of 62.5 mg per cat (10-12 mg / kg) after t = 0, 96, 168 and 240 h. Blood was collected just prior to treatment, as indicated by vertical dotted lines.
Figure 2. Plasma mefloquine concentrations (ug / ml) during the first 24 hours after administration to cats 62.5 mg (10-12 mg / kg) mefloquine at t = 0.
Cat DCat ACat BCat GCat ECat CCat F
HCastrated male Castrated maleCastrated female Castrated female Castrated male Castrated female Castrated female
00.00 0.00 0.00 0.00 0.00 0.00 0.00 
10.54 1.580.31 1.970.22 0.86 - 
20.95 1.950.89 2.790.40 2.19- 
41.132.101.843.230.49 - - 
81.592.232.202.890.64 - - 
121.772.972.143.220.72 - - 
242.93.352.93.120.56 - - 
481.863.341.972.880.56 - - 
961.512.761.752.500.57 - - 
1682.754.153.363.733.58- 1.39
2401.856.512.934.944.20- 1.54
3363.74.193.604.562.9- 2.11
Table 1. Plasma mefloquine concentrations in individual cats (ug / ml). Cats C and F were excluded from the pharmacokinetic analysis (PK) due to incomplete data. Cat C was excluded from the study due to vomiting, while cat F vomited after the first dose, but was successfully re-enrolled in the study on the second day of treatment. Cat E was excluded from the PK analysis because the profile of this cat was remote and distorted the data.

Pharmacokinetic (PK) parameters are shown in Table 2. Cats C and F were excluded from the PK analysis due to incomplete data. Because the PK profile of cat E distorts the data, indices for four cats (cat A, B, D, and G) with more consistent profiles were used for analysis. 

PK indices Units Average SD Median MinMax
ke (48-96 h)1 / h0.0030.0010.0030.0030.005
t1 / 2h224.1851.60233.94153.24275.60
Tmaxh15.0010.5216.004.0024.00
Cmaxμg / ml2.710.662.712.093.35
AUC 0-96 hμg / ml × h228.3062.23228.18166.59290.25
AUMC 0-96 hμg / ml × h 2107372971.7105767826.013968
MRT 0-96 hh326.5013.60337.46221.17397.47
V / Fobs (calculated 0-96 h)L / kg17.414.0815.7414.7323.41
Cl / Fobs (calculated 0-96 h)L / h / kg0.060.020.0520.040.085
Table 2. Pharmacokinetic parameters of cats A, B, D and G during the first 96 hours.
SD - standard deviation; ke - elimination rate constant; t1 / 2 - elimination half-life; Tmax - time to maximum plasma concentration; Cmax - maximum plasma concentration; AUC 0 –96 h- area under the curve for 96 h; AUMC 0-96 h - area under the torque curve during 96 h; MRT 0 –96 h- average residence time; V / Fobs - apparent volume of distribution; Cl / Fobs - Apparent clearance.

Hematology and biochemistry of the serum of six cats (cats A, B, D, E, F and G) were performed before treatment (0 h), after 168 and 336 h. Cat C was excluded from the study after the first two checkpoints and therefore blood collection was not continued. Haematological results were unambiguous at all six time points. The results of biochemistry are shown in Table 3.

0h0h168h168h336h336h
Biochemical analyteUnitsAverageRangeAverageRangeAverageRangeReference interval (Idexx reference laboratory)
Glucosemmol / l––5.103.90-6.304.503.40-5.403.20-7.50
SDMAug / dl6.701.00-8.0011.08.00-13.013.510.0-16.00.00-14.0
Creatinineumol / l11590.0-140.12280.0-160.120.100.-140.80.0-200.
Ureammol / l8.006.80-10.27.706.90-9.108.086.90-9.205.00-15.0
Phosphorusmmol / l1.701.40-2.001.401.17-1.631.321.20-1.600.00-2.30
Calciummmol / l2.402.30-2.502.402.40-2.602.302.20-2.402.10-2.80
Sodiummmol / l152149-153154152-156151148-153144-158
Potassiummmol / l5.104.50-5.204.504.10-5.204.404.10-4.703.70-5.40
Chloridemmol / l115111-117123120-125118116-120106-123
Bicarbonatemmol / l16.015.0-18.0––16.3 (4 cats)15.0-18.012.0-24.0
Anion gapmmol / l25.825.2-27.1––20.6 (4 cats)20.1-21.315.0-31.0
Total proteing / L75.367.0-86.071.065.2-80.771.365.0-83.760.0- 84.0
Albuming / l31.729.0-36.028.927.8-30.030.028.0-32.025.0-38.0
Globuling / L43.735.0-37.042.335.3-52.941.233.0-55.731.0-52.0
ALTU / L79.243.0-16147.326.0-11658.722.0-16619.0-100.
ASTU / L47.825.0-83.029.722.0-53.029.820.0-42.00.00-62.0
ALPU / L39.821.0-75.037.024.0-72.041.827.0-87.05.00-50.0
GGTU / L0.700.00-1.00––0.500.00-2.000.00-5.00
Total bilirubinumol / l3.003.002.100.40-2.702.602.00-3.000.00-7.00
Cholesterolmmol / l3.852.60-4.903.903.00-4.803.100.00-4.702.20-5.50
CKU / L299133-73517897.0-39814817.0-24864.0-400
TT4nmol / l32.521.0-39.032.628.6-36.7 32.4-35.410.0-60.0
Table 3. Biochemical results (mean and range) at 0, 168 and 336 h. Numbers outside the reference intervals are highlighted in bold. Not all biochemical analytes were listed due to the availability of different biochemical analytes in different laboratories, so the fields are blank.
SDMA-symmetric dimethylarginine; ALT-alanine transaminase; AST-aspartate transaminase; ALP-alkaline phosphatase; GGT-gamma-glutamyl transpeptidase; CK-creatine kinase; TT4-total thyroxine. Numbers outside the reference intervals are highlighted in bold.

Biochemical examination showed a trend of increasing SDMA concentrations at 168 and 336 hours in all six cats. One-way repeated measures ANOVA comparing SDMA at all time points was statistically significant p <0.002. Tukey's multiple comparison tests show that the average SDMA value at each time point was statistically different: 0 vs 168 h p = 0.002; 168 vs 336 h p = 0.005. Figure 3 shows the median SDMA concentrations at each time point with upper and lower ranges from six cats. The median SDMA at 0 h was 8.0 g / dl (range 1.0 - 8.0), the median SDMA at 168 h was 11.5 g / dl (range 8.0 - 13.0) and at 336 h was 14 .0 g / dl (range 10.0 - 16.0). Creatinine concentrations did not differ significantly at 0, 168, and 336 h in the six cats. Three cats had elevated liver parameters before treatment, including ALT, AST and ALP. Of these three cats, one cat (Cat G) had an ALT of up to 161 U / L and ALP was 75.0 U / L prior to treatment, and ALT and ALP remained elevated to 166 U / L and 87.0 U / L, respectively. at 336 h. This cat had no side effects during the study. One cat with slightly elevated ALT (142 U / L) was excluded from the study due to vomiting (cat C). Another cat with slightly elevated ALT (144 U / L) and AST (83.0 U / L) before treatment remained clinically healthy throughout the study and both liver parameters returned to normal after 168 and 336 h. Other biochemical analytical changes were unnoticed. Blood glucose was not provided at 0 h because artificial hypoglycemia was observed in all samples. This was suspected to be due to a problematic blood sampling method for glucose determination. 

Figure 3. SDMA results (ug / dl) of six cats at 0, 168 and 336 h. The median SDMA concentration at each time point is displayed with an upper and lower range. The dashed line represents the reference interval (0.00 - 14.0).

Although cats C and F vomited on the first administration of mefloquine, all other cats tolerated the drug well on the next administration when mefloquine was administered with food. No other side effects were observed in any cat during the two weeks of treatment.  

Discussion

This is the first pharmacokinetic study of mefloquine in cats. The only reported use of mefloquine in animals is as an antimalarial for predators and penguins [21,22]. In addition to its use as an antimalarial, successful treatment with this drug has been reported in people with progressive multifocal leukoencephalopathy caused by John Cunningham virus (JCV) [23,24]. Its antiviral activity has been demonstrated in vitro with FCoV [17], feline calicivirus [25], dengue virus type 2 and Zika virus in humans [26] and more recently with pangolin coronavirus GX_P2X, which is a model for SARS-CoV-2, the causative agent COVID-19 in humans [27]. The exact mechanisms of its action as an antimalarial or antiviral agent are not known [17,28,29]. 

As mefloquine is an antimalarial prophylaxis and treatment of humans, its pharmacokinetic profile has been documented. In healthy volunteers, the oral half-life of mefloquine is 1-4 h (mean 2.1 h) [30]. The oral bioavailability of mefloquine in cats is unknown, as the required IV AUC required for calculation has not been performed in cats. However, the oral bioavailability of mefloquine in dogs has been found to be approximately 67-90 % (mean 78 %) [20]. Mefloquine reaches maximum plasma concentrations after approximately 6-24 h (median 17.6 h) in humans [30]. When administered orally to cats, the time to peak plasma concentrations (Tmax) is comparable to humans, averaging 15 hours. The estimated total apparent volume of distribution in healthy humans is approximately 19.2-22.1 l / kg and the systemic clearance is 0.026-0.042 l / h / kg [31], while the apparent mean ± SD volume of distribution in cats is 17.4 ± 4 .08 l / kg and the apparent clearance is 0.060 ± 0.020 l / h / kg when calculated at 0 to 96 h. Plasma protein binding was 98 % in healthy human volunteers and patients with uncomplicated falciparum malaria [30] and also 99 % in cat plasma from clinically normal cats and FIP cat plasma [19]. In humans, the elimination half-life of mefloquine is approximately 20 days in healthy subjects, 10 to 14 days in patients with uncomplicated falciparum malaria [32,33], and 20 days in cases involving severe malaria [33,34]. In humans, a loading dose and then treatment once a week is recommended [35,36]. Mefloquine is slowly excreted from the body via faeces and urine [31,37]. In our study, we estimated that the elimination half-life of mefloquine in clinically healthy cats is approximately 224 hours or approximately 9.3 days, similar to healthy humans. The elimination half-life calculation was based on 24 to 96 h time periods only; further studies, with sampling at a single dose of mefloquine longer than 96 hu in cats, may provide a clearer result.

Oral absorption was increased when mefloquine was administered with food. Pharmacokinetic analysis showed that the mean plasma concentration was higher (4.06 ug / ml) after 240 h when mefloquine was administered with food, compared to the plasma concentration of 2.71 ug / ml after 15 h when mefloquine was administered without food. . Other factors affecting the higher plasma concentrations after 240 hours include the cumulative effect of the drug when administered multiple times and the possible enterohepatic circulation of the drug. In humans, the presence of food in the gastrointestinal tract affects the pharmacokinetic properties of mefloquine by significantly increasing the rate and extent of absorption [38]. 

Mefloquine at 10 μM was shown to show significant inhibition against two FCoV biotypes, FIPV WSU 79-1146 (FIPV1146) and FECV WSU 79-1683 (FECV1683), obtained from the American Type Culture Collection (Virginia, USA), [17] . As the molecular weight of mefloquine is 378 g / mol, a plasma concentration of 10 μM = 3.78 μg / ml is achieved using 10 μM mefloquine [17]. This study showed that a single oral dose of mefloquine ~ 12.5 mg / kg achieved a maximum plasma concentration (Cmax) of 2.71 μg / ml. A higher dose of mefloquine may be required to inhibit FIP. However, it is possible that Cmax will be much higher when mefloquine is administered with food, as reported after 12 to 24 hours. The evaluation of the efficacy of mefloquine against FCoV deserves a clinical study. In addition, mefloquine has been shown to inhibit cytopathic effects in cells infected with SARS-CoV-2a coronavirus (GX_P2X), making it a potential drug for use in cats with SARS-CoV-2 infection [27].

Chloroquine, a 4-aminoquinoline with a similar mode of action to mefloquine [39], has shown an inhibitory effect against FIPV replication and an anti-inflammatory effect in vitro and improved the clinical evaluation of experimentally induced FIP in cats [40]. Although mefloquine has been shown to inhibit FIPV in vitro [17], its clinical efficacy in cats with FIP remains unknown. However, chloroquine caused an increase in ALT levels when used in FIP-infected cats. In this study, mefloquine did not increase ALT levels. Although some cats had elevated ALT levels prior to the mefloquine dose, no further increase was observed after four doses of mefloquine twice a week. Hydroxychloroquine has been studied in a clinical study for the treatment of COVID-19 in humans [41] and its antiviral properties against FIPV in vitro have also been recently investigated [42]. At when used with recombinant feline IFN-ω, hydroxychloroquine has shown increased antiviral activity against FIPV infection [42]. Further clinical studies are needed to verify its clinical efficacy and safety in cats with coronavirus or calicivirus infection. Side effects of mefloquine in humans are common, with 47-90 % people having some mild to moderate side effects [30,43,44]. The incidence of adverse events decreases with long-term use, from 44 % during the first 4 months to 19 % after one year [30,45]. The most common side effects include neuropsychiatric effects [46-48], gastrointestinal dysfunction [49], dermatological symptoms [50], haematological changes [51] or cardiovascular dysfunction [30,33]. In humans, nausea and vomiting are common side effects and may be dose and age dependent, with younger children being most at risk [49,52]. In this study, two cats vomited after the first administration of mefloquine without food. One cat (cat F) was successfully re-administered mefloquine after feeding and was therefore re-enrolled in the study. Cat C was also re-administered a second dose of mefloquine (day 4); however, this cat refused food before the second dose. Mefloquine was therefore dosed without food. This cat vomited again and was excluded from the study. No further vomiting was observed when mefloquine was administered with food. No other clinical side effects were observed in cats in our study. However, our cats were observed for only 14 days. Any delayed or long-term side effects of mefloquine in cats remain unknown. It is also possible that the incidence of side effects could be reduced with long-term administration, as observed in humans [30,45]. 

The cause of the lower plasma concentration curve of Cat E during the first dosing interval (0-96 h) remained unknown (Figures 1 and 2). The age difference may explain the lower plasma concentration curve of cats D and E, as these two cats are younger than the others (3 years versus 6-7 years). Decreased hepatic clearance, increased volume of lipid-soluble drugs with extended half-lives and increased oral bioavailability have been proposed to explain why older people have different pharmacokinetics compared to younger adults, and these causes could potentially contribute to differences in cat plasma concentrations. D and E [53,54]. However, no increase in volume of distribution and prolonged half-life were observed in older cats (cats A, B, C and G). Although human mefloquine blood levels during pregnancy are lower than in non-pregnant adults, there were no age-related differences in plasma mefloquine concentrations in the pharmacokinetic profiles [55,56]. Interestingly, maximum blood concentrations are 2-3 times higher in Asian adults compared to non-Asian volunteers, and the reason for this ethnic difference is unclear [30,57]. It is thought that a lower volume of distribution may have contributed to higher plasma concentrations due to lower body fat or differences in enterohepatic drug circulation in Asian volunteers [58]. In our study, it was not possible to identify differences in plasma concentrations between gender, castration, and body weight. Cat E also had normal biochemical analytes before treatment, at 168 and 336 h. Liver dysfunction causing altered drug metabolism is unlikely; however, it cannot be completely ruled out without determining bile acid levels before and after treatment to assess liver function. In humans, mefloquine is metabolised by cytochrome P450 3A (CYP 3A) in the liver [59]. In cats, CYP 3A activity was found to be lower in cats compared to cats [60]. However, the special plasma concentration curve of cat E cannot be explained. Another explanation could be that cat E could vomit without being observed after the first administration of mefloquine. 

The difference in pharmacokinetic profile is observed in healthy people compared to malaria-infected people. In humans, plasma mefloquine concentrations are 2-3 times higher in uncomplicated falciparum malaria compared to healthy volunteers. Uncomplicated malaria falciparum also has a shortened half-life [30,31,33,61]. The cause is not fully understood. One possible cause of the shortened half-life in patients with malaria is a decrease in enterohepatic circulation and greater fecal clearance. Another explanation for the differences in pharmacokinetic profile between the two groups is the difference in mefloquine binding to plasma proteins. Mefloquine is highly bound to plasma proteins, especially acute phase proteins such as alpha-1-acid glycoprotein (AGP) [62]. An increase in AGP in malaria is thought to lead to an increase in plasma protein binding of mefloquine, which affects the apparent volume of distribution [61]. High levels of AGP have been demonstrated in experimentally induced FIP [63] and naturally infected cats with FIP [64,65] and are commonly used in practice as a diagnostic tool for FIP [66]. Thus, it is possible that high levels of AGP and potentially other acute phase proteins in FIP-infected cats increase mefloquine binding to plasma proteins, altering the pharmacokinetic profile in these cats. Plasma protein binding of mefloquine in clinically normal and FIP-infected cats was investigated in vitro; however, the difference was ambiguous due to the unknown biological variability of the assay [19]. Further studies on the pharmacodynamics and pharmacokinetics of mefloquine are required in cats with FIP. 

During this study, a trend of increasing SDMA without a change in creatinine was observed in all cats (Figure 3). SDMA has been shown to be an early renal biomarker compared to creatinine [67-69] and increases in acute renal injury and chronic kidney disease [70]. Elevated serum SDMA concentrations in cats have been associated with decreased renal function as measured by glomerular filtration rate (GFR) [71]. Based on the results of our study, it is possible that mefloquine may cause decreased renal function in cats. Renal toxicity from antimalarial administration is rare in humans [72]. Another explanation for the elevated SDMA concentrations is the effect of general anesthesia and the cumulative effect of isoflurane during the study. Serum SDMA levels measured after induction of anesthesia (17.11 g / dl) have been shown to be significantly higher than levels measured before induction of anesthesia (12.39 g / dl) [73]. As cats were anesthetized with isoflurane during blood collection, this could potentially contribute to increased SDMA concentrations. Blood collection, mefloquine dosing, and cat recruitment were commissioned from an external designated animal research facility (Invetus Pty, Ltd., Casino, NSW, Australia) due to lack of subject availability, and this study was performed according to Invetus standard operating procedures. 

One limitation of this study was that not all cats had normal liver enzymes prior to treatment. Three cats had elevated ALT, AST and ALP levels before treatment. Because blood collection, pre-treatment blood tests, and treatment were performed at an external facility, investigators were unaware of elevated liver parameters prior to treatment. Investigators were also not involved in the recruitment process for these cats and the drug history and previous records of these cats were not known. Nevertheless, there was no significant increase in ALT and ALP after mefloquine treatment. ALT and ALP remained unchanged after 336 hours in one cat (cat G). The plasma mefloquine concentration curve in cat G did not differ significantly from the other cats (cats A, B and D). 

Another limitation is the small number of cats in our study. Only five cats had complete mefloquine plasma concentrations, and only four cats were included in the pharmacokinetic analysis (the low cat E concentration curve was omitted). Despite the small number of cats used in the analysis, an important description of the mefloquine drug profile in a clinically normal cat was provided. This preliminary information is crucial for all other research projects that involve the use of mefloquine in cats. 

Conclusions

The study provides preliminary data on the pharmacokinetic profile of mefloquine in cats and provides useful information for planning clinical trials of mefloquine for the treatment of cats with feline coronavirus (including FIP) and feline calicivirus infections and, if necessary, COVID-19 to potentially reduce virus shedding. . Further studies on its therapeutic effects are needed to determine the therapeutic benefit of mefloquine in cats with these diseases.

Author's contributions: Conceptualization, JMN and MG; methodology, MG and BK; software, BK and MG; validation, MG and BK; formal analysis, MG and BK; investigation, MG, BK and JY; sources, MG and BK; data curators, MG, JY and BK; preparation of the original proposal, JY; writing - review and editing, JY, MG and JMN; visualization, MG and JY; supervision, JMN and MG; project administration, MG; fundraising, JMN, MG and BK All authors have read and agreed to the published version of the manuscript.

Financing: This research was funded by the Winn Feline Foundation, grant number 2019_027, a donation from the estate of Christine Gai Atkins and a reference from Lesley Muir of the Sydney School of Veterinary Science.

Acknowledgments: The authors are grateful to Invetus for supporting the recruitment of cats, providing shelter, medication and taking the blood of cats.

Conflict of interests: The authors do not indicate any conflict of interest. The funders did not participate in the study design, data collection, analysis or interpretation, manuscript writing or decision to publish the results.

Some veterinarians around the world are already using mefloquine as an off-label treatment for FIP, while formal research and clinical trials continue.

Dosage according to one of the following researchers: “The dose used is 10 to 12 mg / kg orally twice a week and must be given with a small amount of food to prevent vomiting. This is usually equivalent to Lariam 1/4 250 mg tablets in many cats. The drug shows good penetration into the central nervous system in humans, so we hope that it may be more beneficial for severe neurological cases of FIP. "

Researchers are interested in all cats with FIP in treatment. Please contact me privately via email at defeatfip@verizon.net. Well thank you.

Susan E Gingrich, Founder of the Bria FIP Research Fund, December 12, 2020

Note: The entire pack of Lariam with 8 tablets (each containing 250 mg of mefloquine) costs about CZK 700 (approx. € 27). It would therefore be a very inexpensive form of FIP treatment. A two-week treatment for one cat is therefore cheaper than CZK 100 / € 4.

References

  1. Felten, S .; Hartmann, K. Diagnosis of Feline Infectious Peritonitis: A Review of the Current Literature. Viruses 2019, 11, 1068.
  2. Pedersen, NC; Allen, CE; Lyons, LA Pathogenesis of feline enteric coronavirus infection. J. Feline Med. Surg. 2008, 10, 529–541.
  3. Addie, D .; Belak, S .; Boucraut-Baralon, C .; Egberink, H .; Frymus, T .; Gruffydd-Jones, T .; Hartmann, K .; Hosie, MJ; Lloret, A .; Lutz, H .; et al. Feline infectious peritonitis. ABCD guidelines on prevention and management. J. Feline Med. Surg. 2009, 11, 594–604.
  4. Pedersen, NC A review of feline infectious peritonitis virus infection: 1963–2008. J. Feline Med. Surg. 2009, 11, 225–258.
  5. Pedersen, NC, An update on feline infectious peritonitis: Diagnostics and therapeutics. Vet. J. 2014, 201, 133–141.
  6. Tsai, HY; Chueh, LL .; Lin, CN; Su, BL Clinicopathological findings and disease staging of feline infectious peritonitis: 51 cases from 2003 to 2009 in Taiwan. J. Feline Med. Surg. 2011, 13, 74–80.
  7. Hugo, TB; Heading, KL Prolonged survival of a cat diagnosed with feline infectious peritonitis by immunohistochemistry. Can. Vet. J. 2015, 56, 53–58.
  8. Ishida, T .; Shibanai, A .; Tanaka, S .; Uchida, K .; Mochizuki, M. Use of recombinant feline interferon and glucocorticoid in the treatment of feline infectious peritonitis. J. Feline Med. Surg. 2004, 6, 107–109.
  9. Kim, Y .; Liu, H .; Galasiti Kankanamalage, AC; Weerasekara, S .; Hua, DH; Groutas, WC; Chang, KO; Pedersen, NC Reversal of the progression of fatal coronavirus infection in cats by a broad ‐ spectrum coronavirus protease inhibitor. PLoS Pathog. 2016, 12, e1005531.
  10. Kim, Y .; Mandadapu, SR; Groutas, WC; Chang, KO Potent inhibition of feline coronaviruses with peptidyl compounds targeting coronavirus 3C ‐ like protease. Antiviral Res. 2013, 97, 161–168.
  11. Murphy, BG; Perron, M .; Murakami, E .; Bauer, K .; Park, Y .; Eckstrand, C .; Liepnieks, M .; Pedersen, NC The nucleoside analog GS ‐ 441524 strongly inhibits feline infectious peritonitis (FIP) virus in tissue culture and experimental cat infection studies. Vet. Microbiol. 2018, 219, 226–233.
  12. Pedersen, NC; Kim, Y .; Liu, H .; Galasiti Kankanamalage, AC; Eckstrand, C .; Groutas, WC; Bannasch, M .; Meadows, JM; Chang, KO Efficacy of a 3C ‐ like protease inhibitor in treating various forms of acquired feline infectious peritonitis. J. Feline Med. Surg. 2018, 20, 378–392.
  13. Pedersen, NC; Perron, M .; Bannasch, M .; Montgomery, E .; Murakami, E .; Liepnieks, M .; Liu, H. Efficacy and safety of the nucleoside analog GS ‐ 441524 for the treatment of cats with naturally occurring feline infectious peritonitis. J. Feline Med. Surg. 2019, 21, 271–281.
  14. Hsieh, LE; Lin, CN; Su, BL; Jan, TR; Chen, CM; Wang, CH; Lin, DS; Lin, CT; Chueh, LL, Synergistic antiviral effect of Galanthus nivalis agglutinin and nelfinavir against feline coronavirus. Antiviral Res. 2010, 88, 25–30.
  15. Strasfeld, L .; Chou, S., Antiviral drug resistance: Mechanisms and clinical implications. Infect. Dis. Clin. North. Am. 2010, 24, 413–437.
  16. Radford, AD; Addie, D .; Belak, S .; Boucraut-Baralon, C .; Egberink, H .; Frymus, T .; Gruffydd-Jones, T .; Hartmann, K .; Hosie, MJ; Lloret, A .; Lutz, H .; Marsilio, F .; Pennisi, MG; Thiry, E .; Truyen, U .; Horzinek, MC, Feline calicivirus infection. ABCD guidelines on prevention and management. J. Feline Med. Surg. 2009, 11 (7), 556–564.
  17. McDonagh, P .; Sheehy, PA; Norris, JM Identification and characterization of small molecule inhibitors of feline coronavirus replication. Vet. Microbiol. 2014, 174, 438–447.
  18. Izes, AM; Kimble, B .; Norris, JM; Govendir, M. In vitro hepatic metabolism of mefloquine using microsomes from cats, dogs and the common brush ‐ tailed possum (Trichosurus vulpecula). PLoS One 2020, 15, e0230975.
  19. Izes, AM Comparative studies of in vitro hepatic metabolism of mefloquine by feline microsomes and those of other selected species. PhD Thesis, The University of Sydney, Camperdown, NSW, Australia, November 2019.
  20. Schwartz, DE; Weber, W .; Richard-Lenoble, D .; Gentilini, M., Kinetic studies of mefloquine and of one of its metabolites, Ro 21‐5104, in the dog and in man. Acta. Too much. 1980, 37, 238–242.
  21. Remple, JD Intracellular Hematozoa of Raptors: A Review and Update. J. Avian Med. Surg.2004, 18, 75– 88.
  22. Grill, ML; Vanstreels, RE; Wallace, R .; Garcia-Parraga, D .; Braga, EM; Chitty, J .; Catao-Dias, JL; Madeira de Carvalho, LM Malaria in penguins - current perceptions. Avian Pathol. 2016, 45, 393–407.
  23. Hamaguchi, M .; Suzuki, K .; Fujita, H .; Uzuka, T .; Matsuda, H .; Shishido-Hara, Y .; Arai, S .; Nakamura, T .; Kikuchi, S .; Nakamichi, K .; et al. Successful treatment of non ‐ HIV progressive multifocal leukoencephalopathy: Case report and literature review. J. Neurol. 2020, 267, 731–738.
  24. Nambirajan, A .; Suri, V .; Kataria, V .; Sharma, MC; Goyal, V. Progressive multifocal leukoencephalopathy in a 44 ‐ year old male with idiopathic CD4 + T ‐ lymphocytopenia treated with mirtazapine and mefloquine. Neurol. India 2017, 65, 1061–1064.
  25. McDonagh, P .; Sheehy, PA; Fawcett, A .; Norris, JM, Antiviral effect of mefloquine on feline calicivirus in vitro. Vet. Microbiol. 2015, 176, 370–377.
  26. Balasubramanian, A .; Teramoto, T .; Kulkarni, AA; Bhattacharjee, AK; Padmanabhan, R. Antiviral activities of selected antimalarials against dengue virus type 2 and Zika virus. Antiviral Res. 2017, 137, 141–150.
  27. Fan, HH; Wang, LQ; Liu, WL; An, XP; Liu, ZD; He, XQ; Song, LH; Tong, YG Repurposing of clinically approved drugs for the treatment of coronavirus disease 2019 in a 2019 ‐ novel coronavirus (2019nCoV) related coronavirus model. Chin. Med. J. (Engl) 2020, 133 (9), 1051–1056.
  28. Brickelmaier, M .; Lugovskoy, A .; Kartikeyan, R .; Reviriego-Mendoza, MM; Allaire, N .; Simon, K .; Frisque, RJ; Gorelik, L. Identification and characterization of mefloquine efficacy against JC virus in vitro. Antimicrob. Agents Chemother. 2009, 53, 1840–1849.
  29. Owen, A .; Janneh, O .; Hartkoorn, RC; Chandler, B .; Bray, PG; Martin, P .; Ward, SA; Hart, CA; Khoo, SH; Back, DJ In vitro synergy and enhanced murine brain penetration of saquinavir coadministered with mefloquine. J. Pharmacol. Exp. Ther. 2005, 314, 1202–1209.
  30. Palmer, KJ; Holliday, SM; Brogden, RN Mefloquine. A review of its antimalarial activity, pharmacokinetic properties and therapeutic efficacy. Drugs 1993, 45, 430–475.
  31. Karbwang, J .; White, NJ, Clinical pharmacokinetics of mefloquine. Clin. Pharmacokinet. 1990, 19, 264–279.
  32. Desjardins, RE; Pamplin, CL, 3rd; von Bredow, J .; Barry, KG; Canfield, CJ Kinetics of a new antimalarial, mefloquine. Clin. Pharmacol. Ther. 1979, 26, 372–379.
  33. Karbwang, J .; Na ‐ Bangchang, K., Clinical application of mefloquine pharmacokinetics in the treatment of P falciparum malaria. Fundam. Clin. Pharmacol. 1994, 8, 491–502.
  34. Juma, FD; Ogeto, JO Mefloquine disposition in normals and in patients with severe Plasmodium falciparum malaria. Eur. J. Drug Metab. Pharmacokinet. 1989, 14, 15–17.
  35. Tan, KR; Arguin, PM; Arguin, T. Travel related infectious disease. In Centers for Disease Control and PRevention. CDC Yellow Book 2020: Health information for international travel Available online: https://www.cbc.gov/malaria/travelers/drugs.html (Accessed on 21st April2020)
  36. Centers for Disease Control and Prevention, Malaria, how to choose a drug to prevent Malaria. Available online: https://www.cdc.gov/malaria/travelers/drugs.html (accessed on 21st April 2020).
  37. White, NJ Clinical pharmacokinetics of antimalarial drugs. Clin. Pharmacokinet. 1985, 10, 187–215.
  38. Crevoisier, C .; Handschin, J .; Barre, J .; Roumenov, D .; Kleinbloesem, C. Food increases the bioavailability of mefloquine. Eur. J. Clin. Pharmacol. 1997, 53, 135–139.
  39. Anthony, HA; Parija, SC Antimalarial drug resistance: An overview. Too much. Parasitol. 2016, 6, 30–41.
  40. Takano, T .; Katoh, Y .; Doki, T .; Hohdatsu, T. Effect of chloroquine on feline infectious peritonitis virus infection in vitro and in vivo. Antiviral Res. 2013, 99, 100–107.
  41. Lundstrom, K. Coronavirus Pandemic ‐ Therapy and Vaccines. Biomedicine 2020, 8, 109.
  42. Takano, T .; Satoh, K .; Doki, T .; Tanabe, T .; Hohdatsu, T. Antiviral Effects of Hydroxychloroquine and Type I Interferon on In Vitro Fatal Feline Coronavirus Infection. Viruses 2020, 12, 576.
  43. Lobel, HO; Bernard, KW; Williams, SL; Hightower, AW; Patchen, LC; Campbell, CC Effectiveness and tolerance of long ‐ term malaria prophylaxis with mefloquine. Need for a better dosing regimen. JAMA 1991, 265, 361–364.
  44. Tin, F .; Hlaing, N .; Lasserre, R. Single ‐ dose treatment of falciparum malaria with mefloquine: Field studies with different doses in semi ‐ immune adults and children in Burma. Bull. World Health Organ. 1982, 60, 913– 917.
  45. Lobel, HO; Miani, M .; Eng, T .; Bernard, KW; Hightower, AW; Campbell, CC Long ‐ term malaria prophylaxis with weekly mefloquine. Lancet 1993, 341, 848–851.
  46. Gribble, FM; Davis, TM; Higham, CE; Clark, A .; Ashcroft, FM The antimalarial agent mefloquine inhibits ATP ‐ sensitive K ‐ channels. Br. J. Pharmacol. 2000, 131, 756–760.
  47. Ringqvist, A .; Bech, P .; Glenthoj, B .; Petersen, E. Acute and long ‐ term psychiatric side effects of mefloquine: A follow ‐ up on Danish adverse event reports. Travel Med. Infect. Dis. 2015, 13, 80–88.
  48. Ritchie, EC; Block, J .; Nevin, RL Psychiatric side effects of mefloquine: Applications to forensic psychiatry. J. Am. Acad. Psychiatry Law 2013, 41, 224–235.
  49. Lee, SJ; Ter Kuile, FO; Price, RN; Luxemburger, C .; Nosten, F. Adverse effects of mefloquine for the treatment of uncomplicated malaria in Thailand: A pooled analysis of 19, 850 individual patients. PLoS One 2017, 12, e0168780.
  50. Smith, HR; Croft, AM; Black, MM Dermatological adverse effects with the antimalarial drug mefloquine: A review of 74 published case reports. Clin. Exp. Dermatol. 1999, 24, 249–254.
  51. Stracher, AR; Stoeckle, MY; Giordano, MF Aplastic anemia during malarial prophylaxis with mefloquine. Clin. Infect. Dis. 1994, 18, 263–264.
  52. Magnussen, P .; Bygbjerg, IC Treatment of Plasmodium falciparum malaria with mefloquine alone or in combination with iv quinine at the Department of Communicable and Tropical Diseases, Rigshospitalet, Copenhagen 1982–1988. Day. Med. Bull. 1990, 37, 563–564.
  53. Klotz, U. Pharmacokinetics and drug metabolism in the elderly. Drug Metab. Rev. 2009, 41, 67–76.
  54. Mangoni, AA; Jackson, SH Age ‐ related changes in pharmacokinetics and pharmacodynamics: Basic principles and practical applications. Br. J. Clin. Pharmacol. 2004, 57, 6–14.
  55. Singhasivanon, V .; Chongsuphajaisiddhi, T .; Sabcharoen, A .; Attanath, P .; Webster, HK; Wernsdorfer, WH; Sheth, UK; Djaja Lika, I. Pharmacokinetics of mefloquine in children aged 6 to 24 months. Eur. J. Drug Metab. Pharmacokinet. 1992, 17, 275–279.
  56. Vieira, JL; Borges, LM; Ferreira, MV; Rivera, JG; Gomes Mdo, S. Patient age does not affect mefloquine concentrations in erythrocytes and plasma during the acute phase of falciparum malaria. Braz. J. Infect. Dis. 2016, 20, 482–486.
  57. Karbwang, J .; Bunnag, D .; Breckenridge, AM; Back, DJ The pharmacokinetics of mefloquine when given alone or in combination with sulphadoxine and pyrimethamine in Thai male and female subjects. Eur. J. Clin. Pharmacol. 1987, 32, 173–177.
  58. Looareesuwan, S .; White, NJ; Warrell, DA; Forgo, I .; Dubach, UG; Ranalder, UB; Schwartz, DE Studies of mefloquine bioavailability and kinetics using a stable isotope technique: A comparison of Thai patients with falciparum malaria and healthy Caucasian volunteers. Br. J. Clin. Pharmacol. 1987, 24, 37–42.
  59. Fontaine, F .; de Sousa, G .; Burcham, PC; Duchene, P .; Rahmani, R. Role of cytochrome P450 3A in the metabolism of mefloquine in human and animal hepatocytes. Life Sci. 2000, 66, 2193–2212.
  60. Shah, SS; Sanda, S .; Regmi, NL; Sasaki, K .; Shimoda, M. Characterization of cytochrome P450 ‐ mediated drug metabolism in cats. J. Vet. Pharmacol. Ther. 2007, 30, 422–428.
  61. Reuter, SE; Upton, RN; Evans, AM; Navaratnam, V .; Olliaro, PL Population pharmacokinetics of orally administered mefloquine in healthy volunteers and patients with uncomplicated Plasmodium falciparum malaria. J. Antimicrob. Chemother. 2015, 70, 868–876.
  62. Zsila, F.; Visy, J .; Mady, G .; Fitos, I. Selective plasma protein binding of antimalarial drugs to alpha1 ‐ acid glycoprotein. Bioorg. Med. Chem. 2008, 16, 3759–3772.
  63. Stoddart, ME; Whicher, JT; Harbor, DA Cats inoculated with feline infectious peritonitis virus exhibit a biphasic acute phase plasma protein response. Vet. Rec. 1988, 123, 622–624.
  64. Duthie, S .; Eckersall, PD; Addie, DD; Lawrence, CE; Jarrett, O. Value of alpha 1 ‐ acid glycoprotein in the diagnosis of feline infectious peritonitis. Vet. Rec. 1997, 141, 299–303.
  65. Giordano, A .; Spagnolo, V .; Colombo, A .; Paltrinieri, S. Changes in some acute phase protein and immunoglobulin concentrations in cats affected by feline infectious peritonitis or exposed to feline coronavirus infection. Vet. J. 2004, 167, 38–44.
  66. Paltrinieri, S .; Giordano, A .; Tranquillo, V .; Guazzetti, S. Critical assessment of the diagnostic value of feline alpha1 ‐ acid glycoprotein for feline infectious peritonitis using the likelihood ratios approach. J. Vet. Diagn. Invest. 2007, 19, 266–272.
  67. Hall, JA; Yerramilli, M .; Obare, E .; Yerramilli, M .; Jewell, DE Comparison of serum concentrations of symmetric dimethylarginine and creatinine as kidney function biomarkers in cats with chronic kidney disease. J. Vet. Intern. Med. 2014, 28, 1676–1683.
  68. Charged, MB; Lees, GE; Boggess, MM; Yerramilli, M .; Obare, E .; Yerramilli, M .; Rakitin, A .; Aguiar, J .; Relford, R. Symmetric dimethylarginine assay validation, stability, and evaluation as a marker for the early detection of chronic kidney disease in dogs. J. Vet. Intern. Med. 2015, 29, 1036–1044.
  69. Yerramilli, M .; Farace, G .; Quinn, J .; Yerramilli, M. Kidney disease and the nexus of chronic kidney disease and acute kidney injury: the role of novel biomarkers as early and accurate diagnostics. Vet. Clin. North. Am. Small Anim. Pract. 2016, 46, 961–993.
  70. Dahlem, DP; Neiger, R .; Schweighauser, A .; Francey, T .; Yerramilli, M .; Obare, E .; Steinbach, SML Plasma symmetric dimethylarginine concentration in dogs with acute kidney injury and chronic kidney disease. J. Vet. Intern. Med. 2017, 31, 799–804.
  71. Braff, J .; Obare, E .; Yerramilli, M .; Elliott, J .; Yerramilli, M. Relationship between serum symmetric dimethylarginine concentration and glomerular filtration rate in cats. J. Vet. Intern. Med. 2014, 28, 1699– 1701.
  72. Wiwanitkit, V. Antimalarial drug and renal toxicity. J. Nephropharmacol. 2016, 5, 11–12.
  73. Namba, S .; Kitamura, R .; Amaha, T .; Befu, M .; Zama, T .; Moriwaki, T .; Kumono, S .; Shichijo, S. Impact of general anesthesia on serum symmetric dimethylarginine concentration in cats, American Association of Feline Practitioners Conference 2018, Charlotte, NC, USA, 27th – 30th September 2018

Luna the Savannah Cat's Remarkable Cure From Deadly FIP With GS-441524 (Formerly EVO984)

Original article on the portal pethelpful.com
20.12.2020

DEBRA ROBERTS

Our savannah kittens were diagnosed with fatal feline infectious peritonitis. Luna's story of surviving the disease could only be realized thanks to ongoing research.

Meet Luna

What is FIP in cats? (Our cat, Luna, went to the University of California, Davis, for a brand new FIP drug trial.)
What is FIP? (Our cat, Luna, underwent clinical trials of a new drug at FIP at the University of California, Davis). All photos are the property of Debra Roberts

Our first pet: a beautiful savannah cat

After a thorough survey and education to learn as much as possible about savannah cats, and after choosing a renowned breeder, Luna became a member of our family in March 2017 at the age of 10 weeks. When I picked her up in Boston, she was brave, active, playful, and at first sight brimming with good health. Luna was extremely friendly, fun, quirky, loving, with a strong personality. She exceeded all our expectations regarding the savannah breed. She quickly invaded our home and our hearts as our first darling and exceptional family member.

Luna was to receive her second combination vaccine and undergo a veterinary examination. On April 13, 2017, she received a vaccine that is part of a routine protocol for cats. After receiving the vaccine, Luna refused to eat, slept constantly and was hot to the touch. Her husband and I thought her middle stomach was enlarged, but when I mentioned it to the vet during the visit, she said it was a "normal kitten's belly."

The only abnormal finding during the examination was cardiac murmurs III. degrees that were thought to be benign. The plan was to re-examine the murmur in a few months and consider a possible cardiological examination if the condition did not improve.

Luna's distended abdomen
Luna with an enlarged belly

Luna's diagnosis FIP: At the right time in the right place

The stomach continued to grow and on April 21 we took Luna to the emergency clinic. I looked for the causes of abdominal distension (expansion of the abdomen) in kittens and I also read about infectious peritonitis in cats (FIP). I tried to push the FIP out of my mind; after all, it is not such a common disease. I thought in the worst case, it could be a parasite.

During the examination, the veterinarian sucked fluid from her abdomen and brought a tube with her sample into the room. She was sure that due to the appearance of fluid, anorexia, lethargy and fever of 40.6 ° C, Luna has a moist form of FIP. She told us about the gloomy prognosis, and that Luna had only a few days ahead of her, or maybe two weeks of life. She suggested that we return a few days to consult an internist and discuss some life-extension options and hear a second opinion, or undergo euthanasia if her condition worsened over the weekend.

So on April 24, we met with an expert to hear his independent opinion. Lune underwent an echocardiogram, underwent X-ray and ultrasound examinations, and other blood tests to confirm the diagnosis of FIP. It took a long and exhausting three days. We refused to accept the reality of the loss of our new child. We started looking for all the ways we could save her. FIP is 100% lethal, there is no cure. How is it possible?

There must still be a way to save her. As a nurse in a large teaching hospital, I encounter clinical trials and research. I thought, "I'm sure someone is working for the FIP." During the very long and exhausting weekend of waiting for a specialist, I called and sent e-mails to every major veterinary school I was able to find on the Internet.

Luna's trip to UC Davis for life-saving medicine

To my great surprise, Michael Bannasch of UCD, Dr. Niels Pedersen's assistant, called me on April 23. Dr. Pedersen is a veterinarian, professor and scientist who has been treating FIP since the 1960s. Michael told me about researching and testing a hitherto unapproved drug. We discussed Luna's diagnosis and examinations, and Michael asked me to email him all of Luna's records and test results. On April 24, I received another phone call during which we talked about further tests and the possibility of flying with Luna to Sacramento - if we can get approval for her participation in the experiment.

If successful, Luna would be the first private cat in the world with a naturally acquired FIP to be tested for a new drug. She had high hopes, she was at the perfect age to respond to the new antiviral. Luna would stay at the clinic for 5 to 10 days for drug testing and monitoring.

Time was running out, her condition was getting worse. She had a high fever. Dr. Pedersen told us to stop palliative care (feline interferon omega and prednisone) and to arrive as soon as possible.

We arrived in Sacramento on April 28, seven days after being diagnosed with FIP. Dr. Pedersen acquainted us in detail with the treatment protocol, showed us the graphs, explained the mechanism of action of the drug to stop the replication of the virus. Then we went to the room where Luna was to stay for the next 5-10 days. At that time, she received her first injection and at the same time underwent a thorough examination.

Luna's stay at UC Davis with Dr. Niels Pedersen

The first day of the trial.
First day of testing.

The experimental antiviral drug known as EVO984 / GS-441524 took effect immediately

Luna responded extremely quickly to a drug called 'EVO984' (later called GS-441524). We noticed an immediate reduction in fever and an improvement after the first injection. Luna reacted so well that we could go home on the sixth day. She was to receive injections for at least another 11 weeks. It was like bringing home a healthy, new kitten, a kitten without fever, malaise and an enlarged belly.

At home, I continued to give daily antiviral injections for a total of 12 weeks. Dr. Pedersen guided us throughout the treatment and advised us when to have the local veterinarian repeat the blood tests. Dr. Pedersen evaluated the results at the same time as regular weight checks to allow the dose to be adjusted accordingly.

By the way, this was the second drug testing at FIP since 2016, which took place at UCD. The first drug, GC376, was able to bring five out of 20 cats that had not relapsed to successful remission. Luna's drug, EVO984 / GS-441524, was even more successful, with approximately 26 cats achieving complete remission, which later changed to "cured."

To read more about FIP drug testing at UCD and the current status of the above antivirals, I recommend the following articles:

Important note: Both researches on UCD are already completed.

Left: Fishbelly, dull, pale coat, piloerection. Middle: five days into the treatment. Right: Abdominal distention rapidly nearly resolved.
Left: large belly, dull, pale coat, piloerection (bristly coat). Wednesday: five days after starting treatment. Right: Abdominal distension is almost gone. Debra Roberts
One year free of FIP.
One year without FIP. Debra Roberts

Happy ending for Luna and hope for cats diagnosed with FIP

On July 23, 2017, Luna received the last injection of EVO984 / GS-441524. She is doing well, showing no signs of illness and her laboratory results are still great. She loves camping and our adventure trips with a backpack on her back. She walked up to 13 miles, either with a harness or on a backpack. You don't see the cat on a leash on the sidewalks or in the camps every day!

Luna has been without FIP for almost four years. He lives a normal and healthy life and enjoys his three savannah friends - Titan, Calypso and Phoebe, which we brought home in October 2017 and November 2018.

Steve Dale, an animal behaviorist and well-known radio personality, interviewed me about Luna's participation in testing a new drug on the program "Steve Dale's Pet World", "In radio interview  (Flash Player required) so you can hear Luna's story.

Luna loves camping and hiking with her human companions

Luna at the Appalachian Trail
Backpacking in Tennessee
Luna (far left) with her siblings from other mothers, Titan, Calypso, and Phoebe

The original article is followed by questions and answers…

en_GBEN